
My most recent PSA results (3.32 ng/mL) have been weighing on me more heavily than I anticipated.
It’s not really the number that bothers me—I knew that it would increase. It’s what to do about that number that has had my mind in overdrive. In many ways, I feel as though I’m back to the weeks after the initial diagnosis sixteen years ago. Hours spent researching. Conflicting approaches to treatment options. Fuzzy definitions and guidelines. Frustration.
The real frustration for me is that none of my numbers or test results fit neatly into any of the guidelines, making decisions for such an important, potentially life-altering treatment even more challenging.
Cancer Staging
I know in the grand scheme of things, this matters very little, but I get frustrated by the inability of the prostate cancer community to clearly define what metastatic prostate cancer is. I’ve asked my medical team multiple times whether my cancer is metastatic, and each time I get a fairly squishy response.
It’s interesting that cancer in the pelvic lymph nodes, N1 using the TNM staging guidelines,1 is classified as Stage IV cancer, yet so many prostate cancer medical professionals say that disease confined to the pelvis really isn’t metastatic disease. Once the cancer is seen beyond the pelvic region, then they classify it as metastatic. Even my own doctors have said as much, and even the FDA thinks cancer in the pelvic region is metastatic and allows the use of ADT + ARPI drugs to treat it.
Of course, then you get to throw in the concept of micrometastases, and that isn’t covered anywhere in the staging guidelines. Yes, your PSA is rising indicating that there’s cancer somewhere, but we just don’t know where. That makes me wonder, if N1 disease in the regional lymph nodes is classified as Stage IV in the TNM guidelines, does that mean that micrometastatic disease should also be classified as Stage IV?
Rather than settling for the, “Kind of, sort of, maybe,” response, my black-and-white thinking mind goes back to the fundamental definition of metastasis:
Metastasis: The spread of cancer cells from the place where they first formed to another part of the body. In metastasis, cancer cells break away from the original (primary) tumor, travel through the blood or lymph system, and form a new tumor in other organs or tissues of the body. The new, metastatic tumor is the same type of cancer as the primary tumor.2
My prostate is gone. The cancer remains elsewhere. Therefore, by definition, I have metastatic prostate cancer. Simple concept for a simple mind.
Again, in the grand scheme of things, I suppose that the classification really doesn’t matter. If someone asks about my status, it’s just easier—and more easily understood—to say, “It’s progressed to Stage IV metastatic cancer,” instead of saying, “Do you have a few hours? It’s complicated.”
PSA Doubling Time
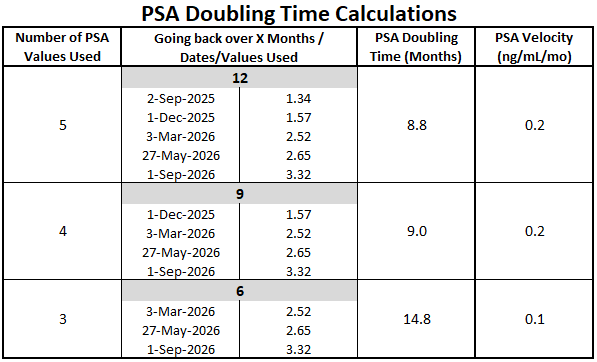
PSA doubling time (PSADT) seems to be an important data point in the decision-making process right now, but even with PSADT, there are disparate views on when to take action.
I’ve seen folks say that you don’t have to act unless your PSADT is less than six months. Others say less than nine months, and yet others say twelve months. If you’ve been following along, you already know that my PSADT has been hovering right around the nine month mark.
Depending on which guideline is used, I’m either late, early, or on the fence when it comes to starting systemic therapy. (And by systemic therapy, I’m talking androgen deprivation therapy with androgen receptor pathway inhibitors (ADT + ARPI).)
Imaging
Having a positive imaging result would certainly drive me to action. But with four 68Ga-PSMA-11 PET scans and one [F18] FDG PET scan not showing any regional or distant metastases, that would suggest that I could tap on the systemic therapy brakes for a while and wait until something does show up, even as my PSA continues to increase.
Balancing it All
So it really comes down to two factors in my mind, and I don’t know which carries more weight in the decision-making process.
Does my PSADT dipping below the nine month threshold carry more weight than negative imaging results and drive me to start systemic therapy? Or do the negative imaging results carry more weight than the PSADT and have me delay starting systemic therapy?
That’s what’s keeping me awake at night. Literally.
Medical Oncologist
I did email my VA medical oncologist (MO) last week after getting my PSA results. In essence, I asked if the jump in my PSA from 2.65 ng/mL to 3.32 ng/mL warranted a change in our plan to have the CT scan and bone scan, and to meet in early December.
In a nutshell, he described the increase as “mild,” and was okay with waiting to meet until December. He also said we could meet earlier if I wanted to.
I’m still processing whether I want to wait or have a conversation sooner. I’ve also thought of reaching out to the UCSD MO as well, and seeking his input on my increase in PSA.
[Actually, in writing this post, distilling how to weigh the two options was a lightbulb 💡 moment for me. I was having difficulty quantifying the problem until writing that a few moments ago, and that’s something to ask both of them.]
Summary
Once again, the act of writing has helped me coalesce my thoughts and ideas, which is good because it was a rough, emotionally draining week for me. Just as I said at the beginning of this adventure, you can research until the cows come home and drive yourself nuts in the process with all the contradictory guidance out there.
Even so, I’m glad I’ve done my homework over that last week or so because I’m much smarter about ADT + ARPI than I was, and that will help me with my discussions with the MO. I know it will happen at some point; it’s just a matter of when.
Time to step away from the computer into our 103° F / 39° C day. Ugh. 🥵
Be well!
Header image: Fishing boats, San Diego Harbor, California


I’d stay the course based on imaging not showing anything. Wait until imaging shows something. Allan
LikeLiked by 1 person
Hi Dan- I’m still around and still following your journey even though the blog seems to have eaten my past few comments. I marvel at the calm, clear way you work through all the variables and keep your wits about you under trying circumstances. I, on the other hand, am a mess for weeks around my 6-month blood draws. I salute you, sir!
Given nothing showing on the scans, I too would lean towards waiting before further treatment. I got through salvage radiation and hormone therapy pretty well, but that was over two years ago, and I’m still a bit heavier with about 15% less T than before. Could be age, and I’m ecstatic that I’ve been undetectable since, but…side effects, man. It’s a balance, though, and you’ve compiled more than enough info to make a intelligent decision for your particular case going forward. All the best, and keep on keeping on!
—J.C.
LikeLike
Hi J.C.,
Thanks for your comment and update. I’m sorry that your previous comments seem to have disappeared into the ether. I’m pretty faithful about approving and responding to them, and I don’t see any of your comments in the spam folder. Odd.
It sounds like you survived hormone therapy relatively well, and who could ask for a better outcome with an undetectable PSA? If you don’t mind me asking, what specific drug(s) did you use for your hormone therapy? Was it ADT alone, or a combination therapy of ADT + ARPI?
I’ve been working on losing some weight ahead of hormone therapy knowing that I’ll likely put some pounds back on during it. It’s been going pretty well so far.
Again, my apologies for your disappearing comments. Wishing you all the best!
Dan
LikeLike
Hi Dan:
I had one dose of Firmagon to drop the T quickly and then, one month later, one (supposedly) three-month dose of Eligard. I was doing well, and even down a few pounds with all the exercise I was doing plus a case of the COVIDs, when I hurt my hip and couldn’t run for a few months. No problem, I thought, my T is on its way back up anyway- I can slack off a bit.
I was wrong.
Long story short, I wound up a few pounds heavier than when this whole thing started. Not a huge amount, and I’m grateful that the overall side effects were limited, but I’m still working to get back to where I was before and have been for about year. Others don’t really notice, but I do.
Anyway, all the best to you,sir. You’re doing all the right things, and I’m hoping a simple, targeted zap will set you straight- and soon.
—J.C.
LikeLike