I discovered the YouTube channel, Grand Rounds in Urology, and it caters most of its content to other doctors. I’ve found some of their videos interesting and educational, but many are over this layperson’s head.
The title of this particular video piqued my interest given my current status, so I sat through all 41 minutes of it. (I wouldn’t say that the video is a “must-watch,” so if you’re looking for something to watch on a rainy night, it might be worth your time.)
In it, the panel reviews several case studies to see how they would approach treating each patient. Very little applied directly to my situation, but it was fascinating to me to watch the conversation, see their thought processes, and hear their different recommended treatment plans.
In one sense, parts of the conversation reminded me of this scene from Raiders of the Lost Ark:
I don’t think that’s new to any of us who have been dealing with this disease for any period of time. You just come to expect that each doctor is going to have their own knowledge base according to their chosen specialty, and they’re going to have their own opinions on how to move forward with treatment. It’s up to us, the patient, to determine which approach aligns best with our own goals and desires.
It’s been a busy time since the last regular monthly post, but in a good way.
I managed to unplug for five days by taking a trip to chase autumn colors in the Eastern Sierra using Bishop, California as my base. I was a week or two early, but still managed to find some good colors. When I returned, I was Mr. Social Butterfly, going to one of the San Diego Padres’ last home baseball games; attending a friend’s birthday party; going to our monthly trivia night with friends at a favorite watering hole; and then watching the Padres beat my hometown Chicago Cubs, all in my first week back. It was good to disconnect and be distracted for a while. I needed that.
Before leaving on my trip, I participated in an online advanced prostate cancer support group run by the AnCan Foundation. (I had featured one of their videos on this blog back in April.) Within the group, there were a few doctors but pretty much everyone else were fellow prostate cancer patients sharing their experiences.
There was a ton of information that was flowing, so it was a tad like trying to take a sip of water from a firehose, but I did come away with some valuable input. Key points included:
Different experiences on different ADT + ARPI drug combinations when it came to side effects. The consensus seemed to be Orgovyx® and darolutamide were the preferred combination.
There was also a recommendation for me to push to get an Axumin PET scan given the four negative PSMA PET scans and the negative [F18] FDG PET scan.
One of the members strongly encouraged me to connect with Dr. Matthew Rettig who operates out of the West Los Angeles VA Medical Center and UCLA. (When I searched on “best prostate cancer medical oncologists in Southern California,” his name was number two on the results.)
They encouraged me to more thoroughly investigate a VA disability rating given the changes in how prostate cancer is addressed under the PACT Act. That’s low on my priority list for a variety of reasons that I won’t go into here.
I have to admit that, given my trip, my social calendar, and my need to unwind from both, I’ve been a bit slow in digesting the meeting’s contents and determining how I want to proceed.
Dr. Rettig’s opinion would be valuable at some point, and I’m just figuring out how and when to do that. I have the CT and bone scans scheduled next month (see below) and, to be honest, I don’t expect that they’ll show anything. I’m thinking that a set of negative results on those scans would give me strong justification for getting an Axumin scan and for the referral to Dr. Rettig. I can say, “I tried what you recommended. Now let’s humor me and find a way to get the Axumin scan.”
The VA can be a bit rigid in its protocols and procedures, and I’m inclined to go through the medical oncologist at VAMC San Diego to get the referral to VAMC West Los Angeles. I don’t want to be stepping on anyone’s toes, or finding out that I’ve inadvertently transferred my full-time care to Los Angeles. (The 147-mile / 236 km drive between home and VAMC WLA is brutal.)
For now, I’m content to wait the six weeks until the scans, get their results, and then push to see Dr. Rettig and go for an Axumin scan if needed. I should have an updated PSA test result at that point, too. Of course, I reserve the right to change my mind. 🙂
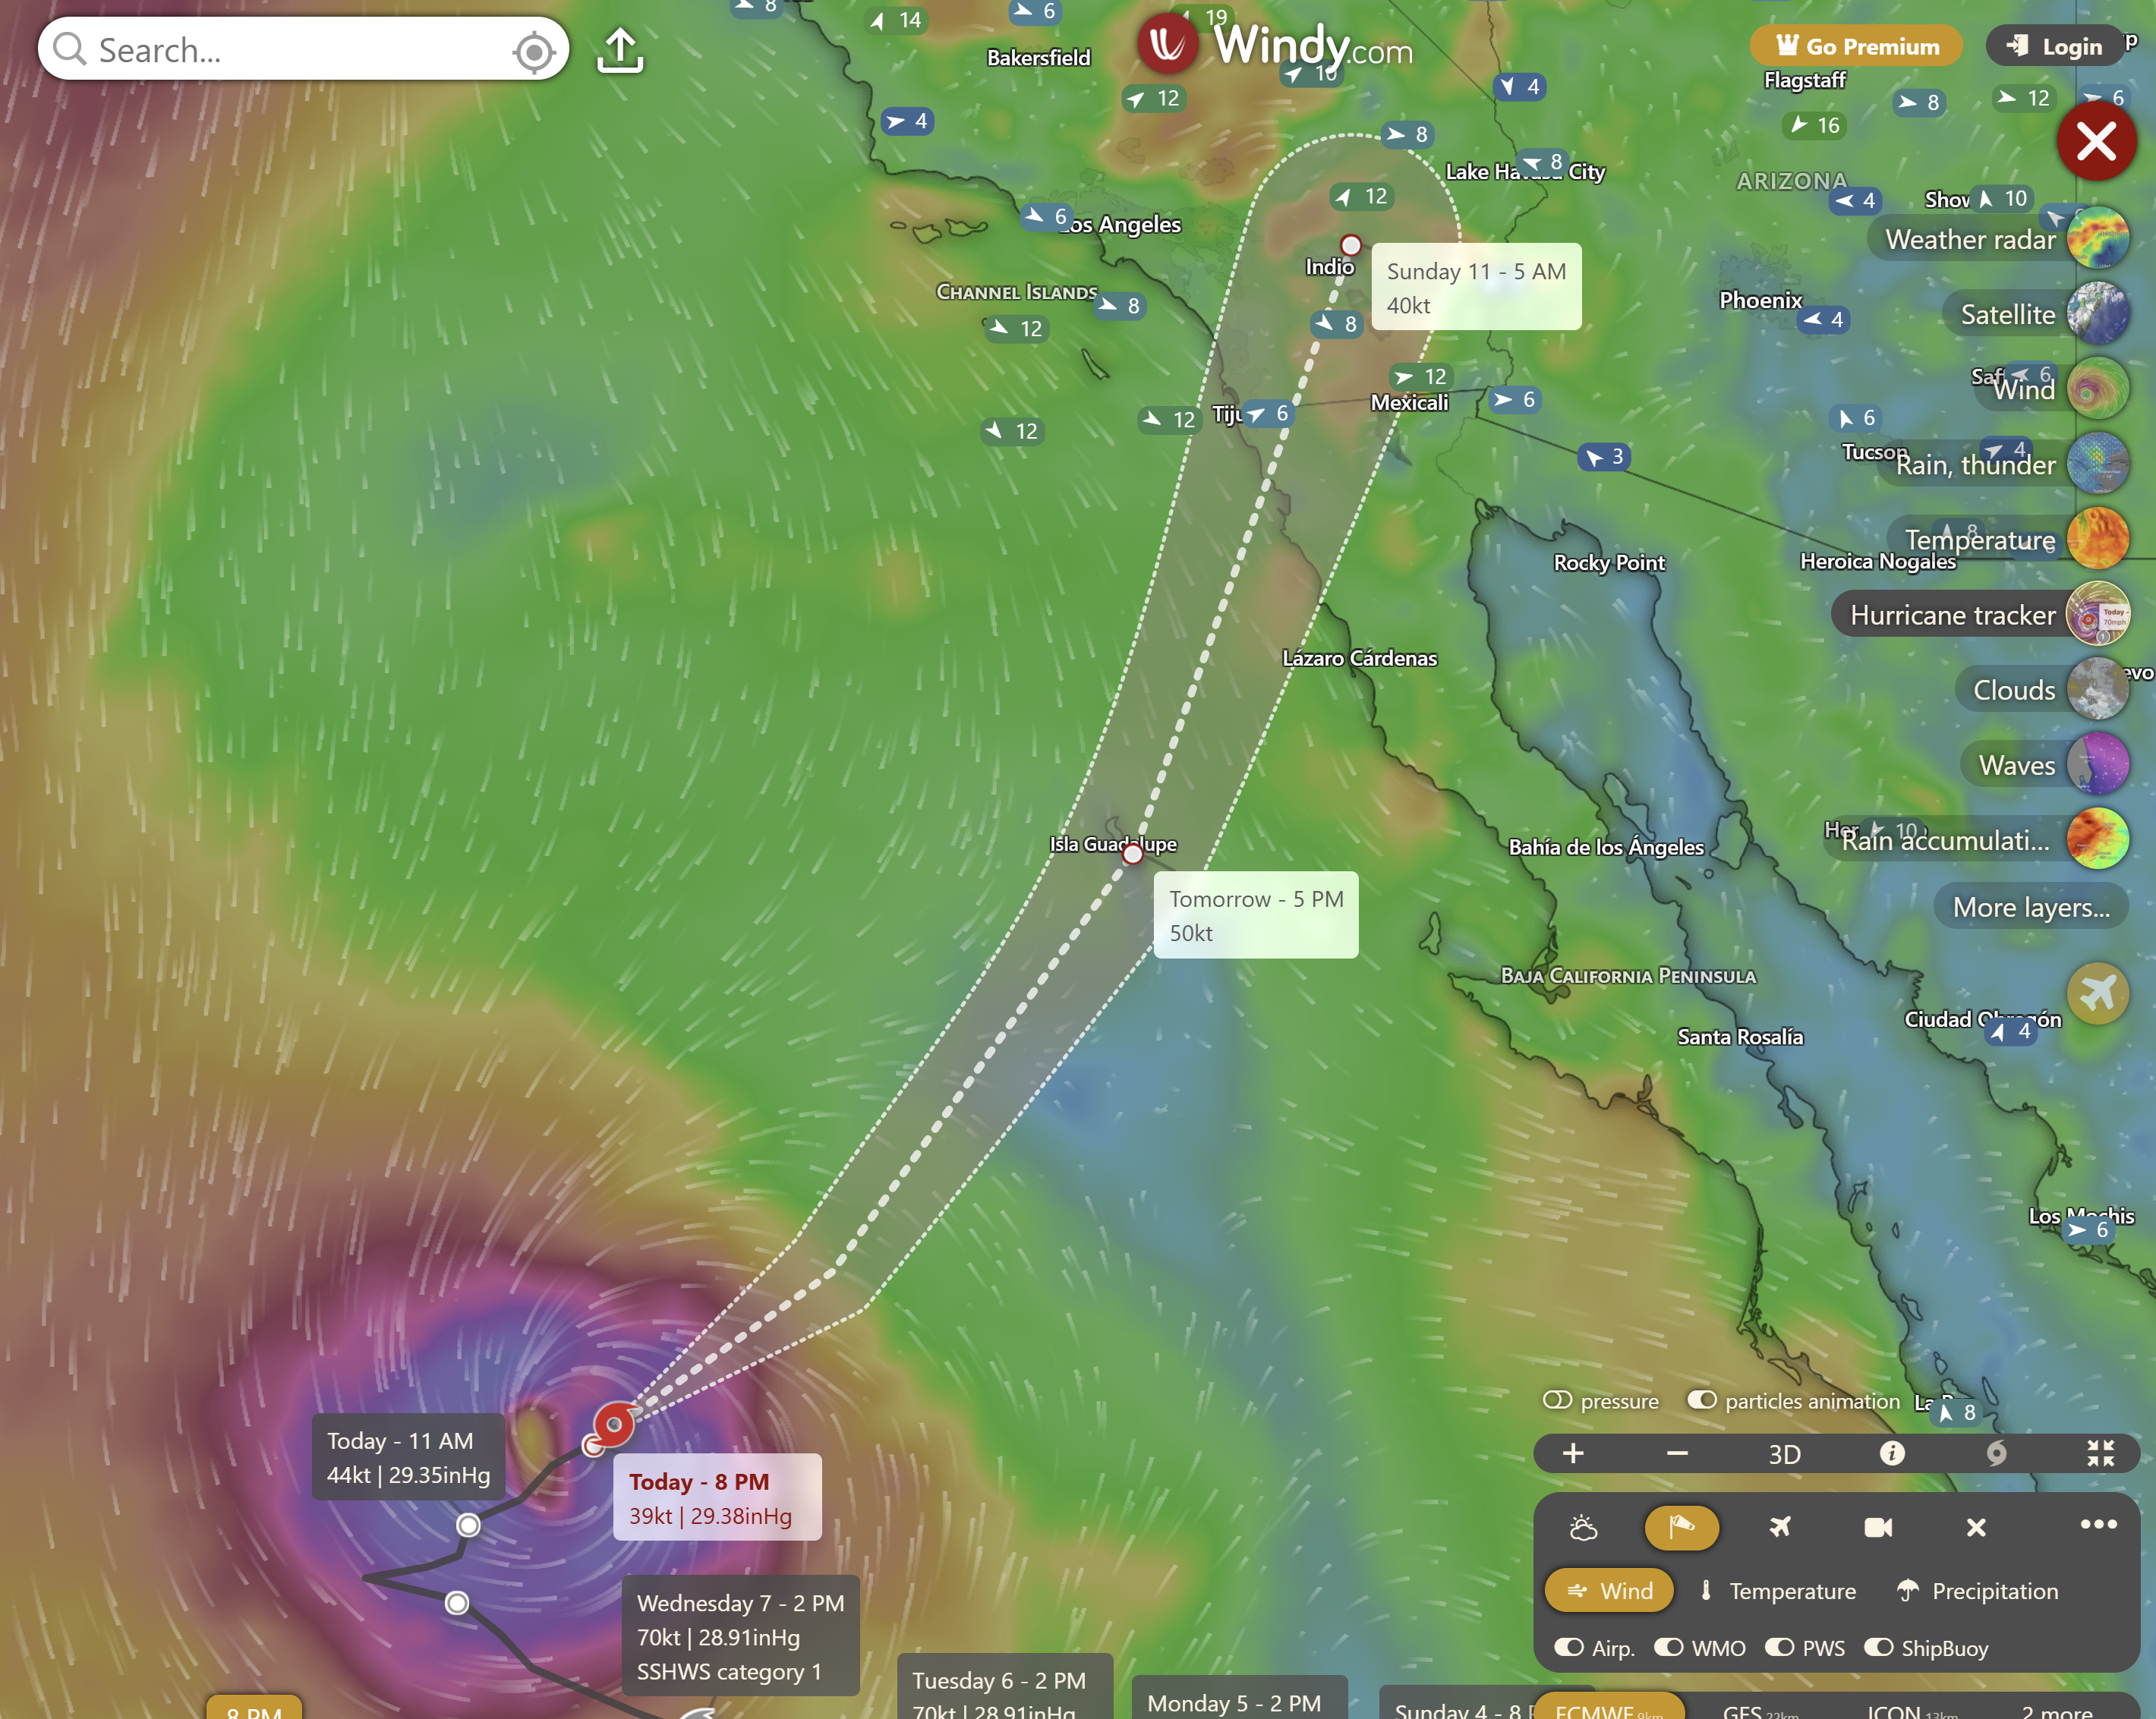
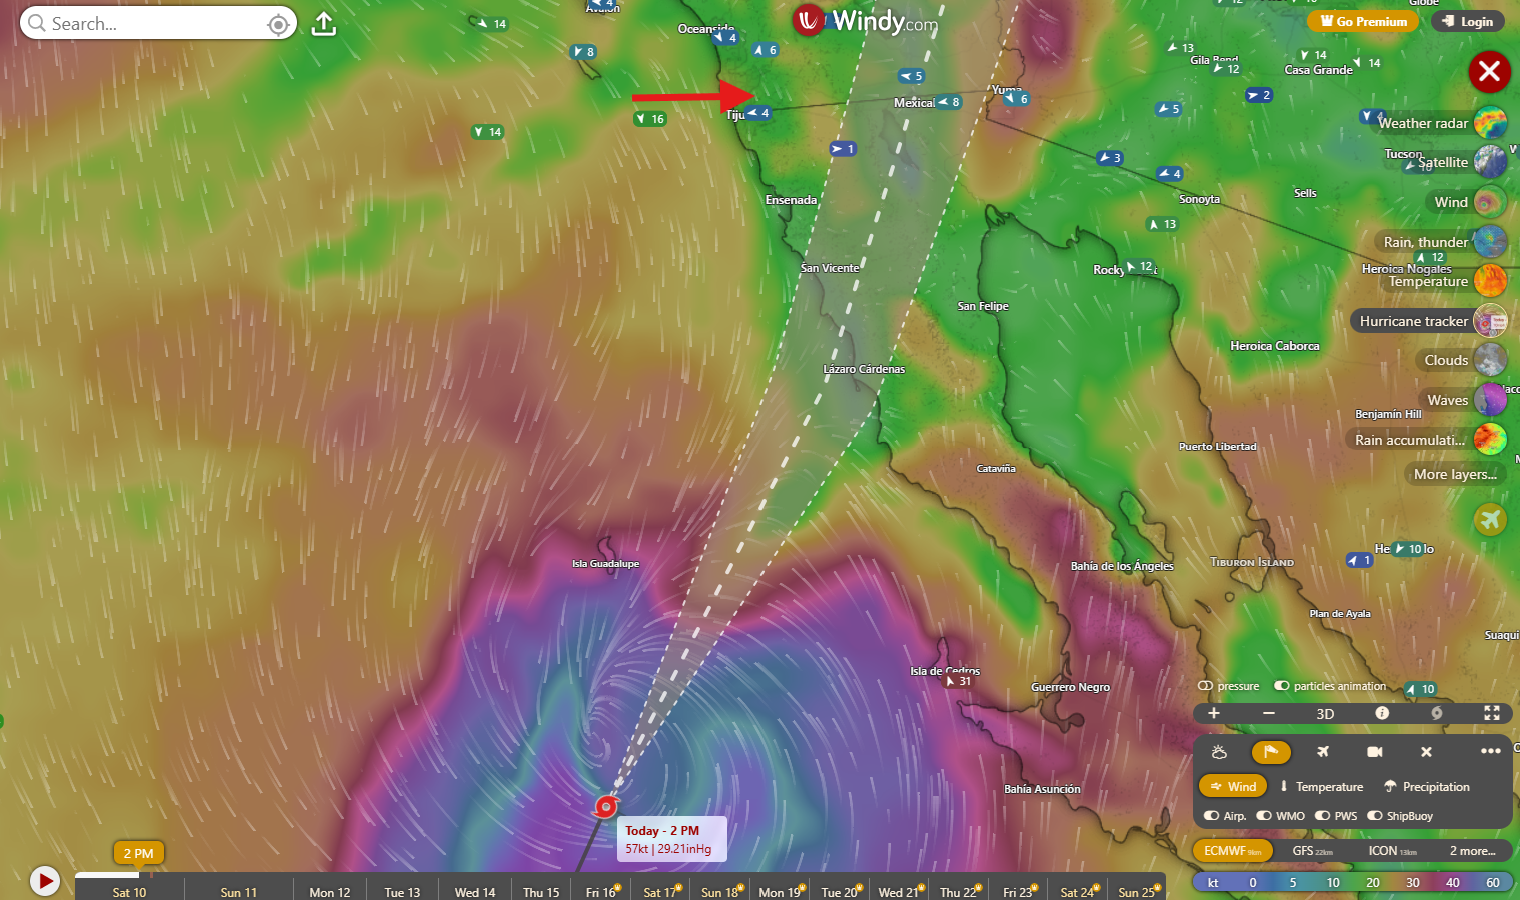
As I’ve been writing this post on Friday night, 9 October, I’ve had one ear open on the forecast for Tropical Storm Rachel, which should be arriving in the San Diego / Tijuana area in about 24 hours. The National Hurricane Center issued a Tropical Storm Watch for San Diego, and this is only the second time ever that a tropical alert has been issued on the west coast. (The last time was in 2023 for Hurricane Hilary. The last time a tropical system actually made landfall on the California coast was 1939.)
UPDATE 5 P.M. PDT, Saturday – Rachel’s forecasted track has moved a bit to the east. Friday night, it was going to pass about 17 miles / 27 km from my house near Tecate; the current track has it passing about 85 miles / 137 km east of my house near Mexicali.
It looks like the brunt of the storm will kick in around 11 p.m. and last through about 10 a.m. tomorrow. One forecast model shows wind gusts in my neighborhood will get up to about 45 mph / 72 km/h. It the mountains east of San Diego, it’s showing they may get up as high as 90 mph / 144 km/h.
The reason I’m so interested in tropical systems is because I rode out Hurricane Iwa which hammered Oahu (where I lived) and Kauai in 1982. It was quite the unnerving experience, About 2 years later, one of the ships I was assigned to got caught up in the periphery of a typhoon while we were at sea, and waves washed away one of our inflatable life rafts. Experience tells me to heed the warnings and take precautions. Better safe than sorry.
Advanced prostate cancer often becomes resistant to treatment with hormone therapies as it advances, and this recent discovery by researchers at the University of Chicago suggests that there may be a way to reverse that resistance:
Current treatment options for treatment-resistant neuroendocrine prostate cancer are largely limited to platinum-based chemotherapies, which offer modest survival benefits. The discovery that tRNA modulation can reverse lineage switching suggests that RNA-targeted therapeutics such as synthetic tRNA mimics or small molecules that enhance tRNAArg (UCU)-1 production, could re-sensitize hard-to-treat tumors to existing, widely available androgen receptor-targeted drugs.
You can find the press release here (it contains a link to the original paper):
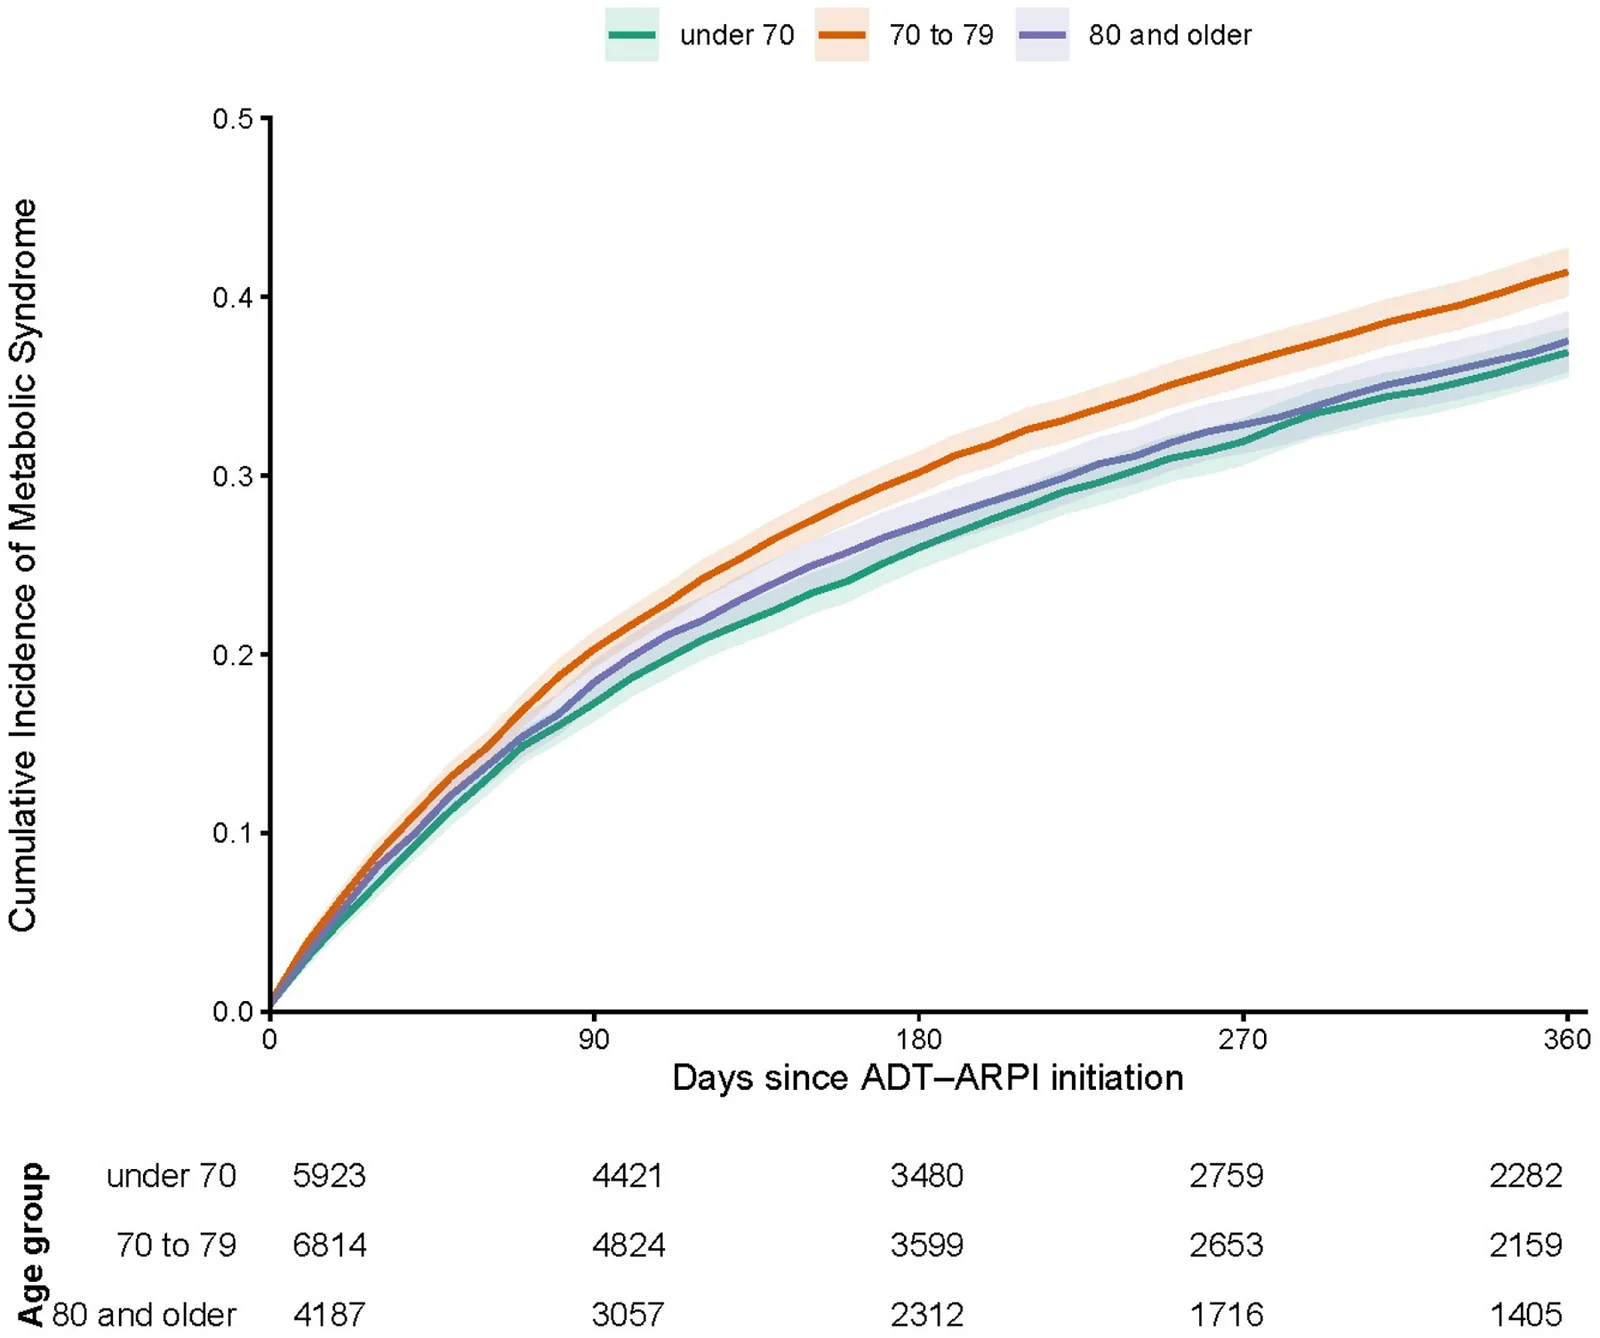
Well, it didn’t take long for last week’s mini vacation to the Eastern Sierra to chase autumn colors to wear off. This article—a distilled version of the original paper—appeared on one of my timelines shortly after I returned. It shows how quickly and how pervasively some of the significant metabolic side effects of ADT + ARPI therapy appear.
Dyslipidemia (unhealthy or unbalanced level of lipids (fats), such as cholesterol or triglycerides, in your blood)
It’s interesting to see that, within 90 days of starting the combination ADT + ARPI therapy, about 15% to 20% of men are experiencing one or more of these side effects, and that number only grows over time, reaching nearly 35% to 40% after a year on treatment.
Cumulative incidence of metabolic syndrome following initiation of concurrent ADT and ARPI therapy, by age group
Shaver AL, Zarrabi KK, Nikita N, Sharma S, Wen KY, Lu-Yao G. Metabolic Dysfunction After Initiation of Androgen Receptor Pathway Inhibitors in Prostate Cancer. JAMA Oncol. 2026 Aug 13:e262790. doi: 10.1001/jamaoncol.2026.2790. Epub ahead of print. PMID: 42593785; PMCID: PMC13474095.
“Hypertension was the most frequently documented outcome,” and that concerns me a bit, as I’m already being treated for hypertension. My blood pressure is currently averaging 106/76, so it’s well-managed on my current treatment plan. It’s a discussion that I’ll have to have when we get to that decision point.
A good follow-up study to this one would be to track how quickly and how far these metabolic syndrome side effects dissipate—if at all—once ADT + ARPI is stopped (i.e., during a hormone therapy holiday).
Be well!
Header image: Minarets near Mammoth Lakes, California
With more trials showing that starting ADT + ARPI hormone therapy early has significant benefits, it’s important to look at the gap between the efficacy and Quality of Life outcomes found in the trials versus what’s happening in the real world.
It’s an interesting discussion that makes you approach starting ADT + ARPI more cautiously.
My most recent PSA results (3.32 ng/mL) have been weighing on me more heavily than I anticipated.
It’s not really the number that bothers me—I knew that it would increase. It’s what to do about that number that has had my mind in overdrive. In many ways, I feel as though I’m back to the weeks after the initial diagnosis sixteen years ago. Hours spent researching. Conflicting approaches to treatment options. Fuzzy definitions and guidelines. Frustration.
The real frustration for me is that none of my numbers or test results fit neatly into any of the guidelines, making decisions for such an important, potentially life-altering treatment even more challenging.
Cancer Staging
I know in the grand scheme of things, this matters very little, but I get frustrated by the inability of the prostate cancer community to clearly define what metastatic prostate cancer is. I’ve asked my medical team multiple times whether my cancer is metastatic, and each time I get a fairly squishy response.
It’s interesting that cancer in the pelvic lymph nodes, N1 using the TNM staging guidelines,1 is classified as Stage IV cancer, yet so many prostate cancer medical professionals say that disease confined to the pelvis really isn’t metastatic disease. Once the cancer is seen beyond the pelvic region, then they classify it as metastatic. Even my own doctors have said as much, and even the FDA thinks cancer in the pelvic region is metastatic and allows the use of ADT + ARPI drugs to treat it.
Of course, then you get to throw in the concept of micrometastases, and that isn’t covered anywhere in the staging guidelines. Yes, your PSA is rising indicating that there’s cancer somewhere, but we just don’t know where. That makes me wonder, if N1 disease in the regional lymph nodes is classified as Stage IV in the TNM guidelines, does that mean that micrometastatic disease should also be classified as Stage IV?
Rather than settling for the, “Kind of, sort of, maybe,” response, my black-and-white thinking mind goes back to the fundamental definition of metastasis:
Metastasis: The spread of cancer cells from the place where they first formed to another part of the body. In metastasis, cancer cells break away from the original (primary) tumor, travel through the blood or lymph system, and form a new tumor in other organs or tissues of the body. The new, metastatic tumor is the same type of cancer as the primary tumor.2
My prostate is gone. The cancer remains elsewhere. Therefore, by definition, I have metastatic prostate cancer. Simple concept for a simple mind.
Again, in the grand scheme of things, I suppose that the classification really doesn’t matter. If someone asks about my status, it’s just easier—and more easily understood—to say, “It’s progressed to Stage IV metastatic cancer,” instead of saying, “Do you have a few hours? It’s complicated.”
PSA Doubling Time
PSA doubling time (PSADT) seems to be an important data point in the decision-making process right now, but even with PSADT, there are disparate views on when to take action.
I’ve seen folks say that you don’t have to act unless your PSADT is less than six months. Others say less than nine months, and yet others say twelve months. If you’ve been following along, you already know that my PSADT has been hovering right around the nine month mark.
Depending on which guideline is used, I’m either late, early, or on the fence when it comes to starting systemic therapy. (And by systemic therapy, I’m talking androgen deprivation therapy with androgen receptor pathway inhibitors (ADT + ARPI).)
Imaging
Having a positive imaging result would certainly drive me to action. But with four 68Ga-PSMA-11 PET scans and one [F18] FDG PET scan not showing any regional or distant metastases, that would suggest that I could tap on the systemic therapy brakes for a while and wait until something does show up, even as my PSA continues to increase.
Balancing it All
So it really comes down to two factors in my mind, and I don’t know which carries more weight in the decision-making process.
Does my PSADT dipping below the nine month threshold carry more weight than negative imaging results and drive me to start systemic therapy? Or do the negative imaging results carry more weight than the PSADT and have me delay starting systemic therapy?
That’s what’s keeping me awake at night. Literally.
Medical Oncologist
I did email my VA medical oncologist (MO) last week after getting my PSA results. In essence, I asked if the jump in my PSA from 2.65 ng/mL to 3.32 ng/mL warranted a change in our plan to have the CT scan and bone scan, and to meet in early December.
In a nutshell, he described the increase as “mild,” and was okay with waiting to meet until December. He also said we could meet earlier if I wanted to.
I’m still processing whether I want to wait or have a conversation sooner. I’ve also thought of reaching out to the UCSD MO as well, and seeking his input on my increase in PSA.
[Actually, in writing this post, distilling how to weigh the two options was a lightbulb 💡 moment for me. I was having difficulty quantifying the problem until writing that a few moments ago, and that’s something to ask both of them.]
Summary
Once again, the act of writing has helped me coalesce my thoughts and ideas, which is good because it was a rough, emotionally draining week for me. Just as I said at the beginning of this adventure, you can research until the cows come home and drive yourself nuts in the process with all the contradictory guidance out there.
Even so, I’m glad I’ve done my homework over that last week or so because I’m much smarter about ADT + ARPI than I was, and that will help me with my discussions with the MO. I know it will happen at some point; it’s just a matter of when.
Time to step away from the computer into our 103° F / 39° C day. Ugh. 🥵
Be well!
Header image:Fishing boats, San Diego Harbor, California
I stumbled across this video on my YouTube feed and found it to be a great overview of many of the trials that are behind the advances in advanced prostate cancer treatment. The video is apparently part of a larger training course for doctors, so it’s not geared toward patients. Even so, I found it informative and (mostly) understandable.
One thing that I found interesting was that there’s an apparent shift away from the use of the word “castration” in describing the state of the disease and treatment options.
The purpose of this was really to ensure that we were trying to be thoughtful around our patients’ feelings around use of the word “castration” and trying to eliminate that from the terminology.
Instead of describing it as “non-metastatic castrate sensitive prostate cancer (nmCSPC)” it’s now called “androgen pathway modulation sensitive (APMS)” or “androgen pathway modulation naïve (APMN).” Once the cancer becomes resistant, it will be called “androgen pathway modulation resistant (APMR).”
To me, it seems as though they want to sugarcoat the hormone therapy experience with these name changes, and the patient may not grasp the full gravity of what’s about to happen to him when he starts this treatment. I’d definitely understand “castration” before understanding “androgen pathway modulation sensitive.” To be fair, it would be interesting to see how many men turn down hormone therapy because they hear the word “castration.” Maybe that’s the driving force behind the name change.
Because Dr. Rettig works with veteran patients at the VA Los Angeles, it was helpful to me to hear some of his insights working with that group.
I overachieved on this post. Normally, reporting PSA results would be quite simple and short. Not this time. The act of writing helps me organize my research and rationalize treatment decisions. Thanks for your indulgence!
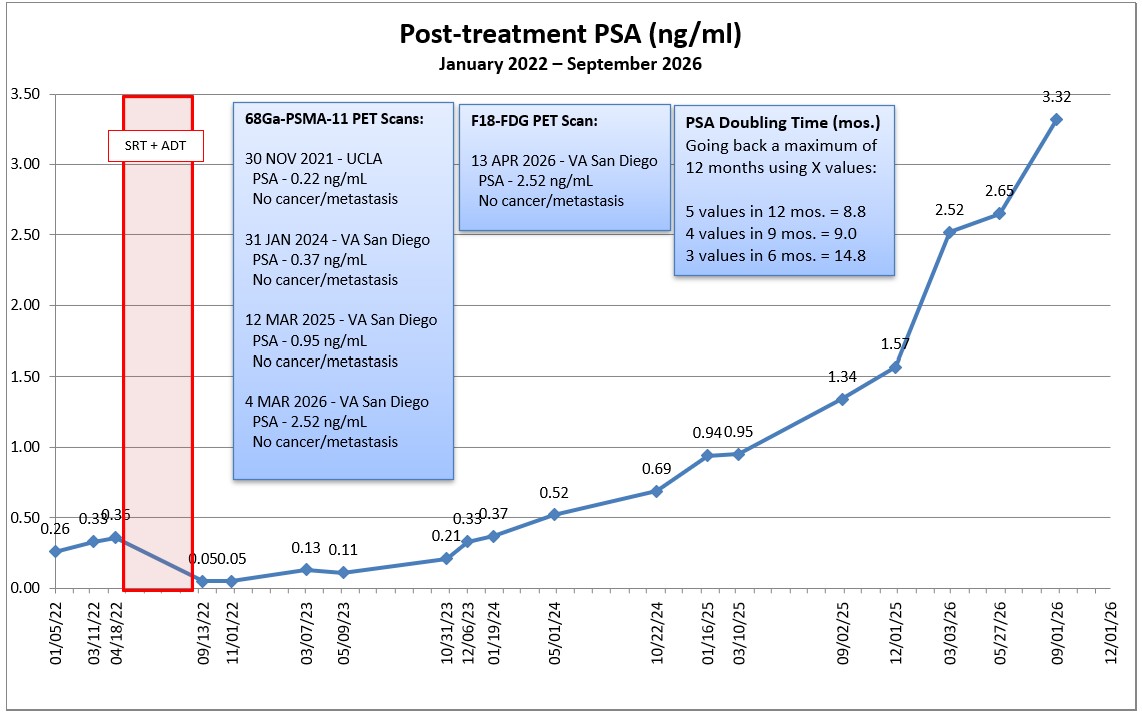
I went for my PSA test this morning, 1 September, and it was 3.32 ng/mL, up from 2.65 ng/mL back in May.
I expected my PSA to go up, and I guessed it would be around 3.0 ng/mL, so the amount it went up was a bit of a surprise. It’s closing in on my PSA level at initial diagnosis, 5.0 ng/mL.
PSA Doubling Time
Seeing as both the VA and UCSD medical oncologists (MO) stressed the importance of using PSA doubling time (PSADT) to guide treatment decisions during my meetings with them in June, I really wanted to try to nail down how it should be calculated.
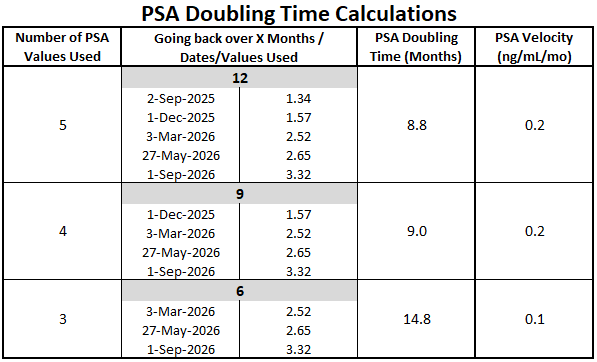
The Memorial Sloan-Kettering PSADT Calculator is a great tool that I’ve been using, but it doesn’t provide any guidance on how many data points should be used over what period of time. I finally found some definitive guidance:
PSA values need not be consecutively rising and all values obtained over a maximum period of 12 months should be included in the calculation. The maximum period of the past 12 months is recommended to reflect the patient’s current disease activity, since in some men PSADT may change over time. Minimum requirements for the calculation are 3 PSA values obtained over 3 months with a minimum of 4 weeks between measurements.1
You can see that I’m sitting right around that nine-month PSADT point that’s the suggested trigger for action. I’m going to keep my mouth shut and ask my MO to calculate the PSADT and see what number they come up with.
Obviously, I’m concerned, but not panicked by this jump in my PSA. I’ll email the MO to see if we should stick to the current plan of having a CT scan on 23 November, or move it to an earlier date. Or to have another PSMA PET scan. In my mind, I’d like to have at least one more scan to try and see if we can determine what we’re dealing with before leaping into combination hormone therapy.
Combination Therapy
The MO’s were really encouraging action if my PSADT was nine months or less because, with faster doubling times, there is high risk of metastasis and prostate cancer-specific mortality. The action that they’re recommending is intermittent combination therapy using androgen deprivation therapy (ADT) plus an androgen receptor pathway inhibitor (ARPI). The specific drugs they’re recommending are Eligard® (leuprolide acetate) (ADT) and Xtandi® (enzalutamide) (ARPI). The Eligard® would stop the production of testosterone, and the Xtandi® would block the cancer cells from absorbing testosterone.
The reason that the MOs want to use the combination therapy is because of the results that were shown in the EMBARK trial. Using Eligard® and Xtandi® together had 87.3% of patients in the trial reach the five-year point metastasis-free. Using just Eligard® alone—the old standard of care—just 71.4% of patients were metastasis-free at five years. The combination therapy won’t prevent progression to metastasis; it just slows it down. This short (2 min.) video from the New England Journal of Medicine gives a good overview:
The combination therapy would be given intermittently, with nine months on the medication and, if my PSA drops to a certain level (usually below 0.2 ng/mL) and stays there, there wouldn’t be a need to restart the combination therapy until there’s a rise in my PSA.
The one thing that I couldn’t find or confirm in my research was if there was a specific PSA level where, if you exceed it, this combination therapy should be started. The UCSD MO seemed okay with waiting until it was as high as 5 to 10 ng/mL if the PSADT didn’t indicate high risk.
Xtandi® (enzalutamide) is just one of several drugs known as Androgen Receptor Pathway Inhibitors (ARPIs). Two others that are commonly used include ERLEADA® (apalutamide) and NUBEQA® (darolutamide). Each has its own similar, but slightly different side effects.
Side Effects / Adverse Events
Messing around with your hormones can have substantial and sometimes debilitating side effects and, when using combination therapy, they can be additive. The National Cancer Institute has defined five grades of adverse events based on their severity:
Grade
Impact
Grade 1
Mild; asymptomatic or mild symptoms; clinical or diagnostic observations only; intervention not indicated.
Grade 2
Moderate; minimal, local or noninvasive intervention indicated; limiting instrumental ADL or mild/moderate impact on age appropriate normal daily activity (pediatric)*.
Grade 3
Severe or medically significant but not immediately life threatening; hospitalization or prolongation of hospitalization indicated; disabling; limiting self-care ADL or severe impact on age appropriate normal daily activity (pediatric)**
Activities of Daily Living (ADL): *Instrumental ADL refers to preparing meals, shopping for groceries or clothes, using the telephone, managing money, etc. **Self-care ADL refers to bathing, dressing and undressing, feeding self, using the toilet, taking medications.
Clearly, a patient would want to steer clear of any Grade 3 or 4 side effects if possible. When you look at the grades of adverse events in the summaries of each of the drugs below, you’ll see that the percentages of patients experiencing an adverse event at all grade levels can be quite high in some cases. Bottom line: ADT + ARPI will adversely impact you and your quality of life in some shape or form. It’s just a matter of degrees.
Some of the possible, more severe side effects include:
Heart disease, stroke, or mini-stroke
Fractures and falls
Lung problems
Seizures
Severe skin reactions
And you can see what percent of the time that patients experienced some of these side effects by adverse event grade in section 6.1 of the prescribing information HERE or in these tables HERE. Some of the Grade 3 or 4 adverse events occurred as much as 8% of the time.
Some of the possible, more severe side effects include:
Heart Disease
Seizure
And you can see what percent of the time that patients experienced some of these side effects by adverse event grade in section 6.1 of the prescribing information HERE. Some of the Grade 3 or 4 adverse events occurred as much as 4% of the time.
Some of the possible, more severe side effects include:
Seizure
Posterior Reversible Encephalopathy Syndrome (PRES) (Involves the brain with seizure or quickly worsening symptoms such as headache, decreased alertness, confusion, reduced eyesight, blurred vision or other visual problems)
Allergic reactions
Heart disease
Falls and bone fractures
Swallowing problems or choking (because of the size of the pills)
And you can see what percent of the time that patients experienced some of these side effects by adverse event grade in section 6.1 of the prescribing information HERE. Some of the Grade 3 or 4 adverse events occurred as much as 9% of the time.
Some of the possible, more severe side effects include:
Heart attack
Elevated blood sugar and increased risk of developing diabetes
Convulsions
And you can see what percent of the time that patients experienced some of these side effects by adverse event grade in section 6.1 of the prescribing information HERE.
Anecdotal Side Effect Experiences
One of the side effects that isn’t specifically mentioned above was cognitive decline. In a study, it was shown:
Patients with advanced prostate cancer treated with enzalutamide (Xtandi) had a significantly greater decline in cognitive function compared with those who received darolutamide (Nubeqa), according to results from a phase II trial.
Median cognitive change in the maximally changed cognitive domain (MCCD) from baseline to 24 weeks was -15.8% for those receiving darolutamide versus -36.1% for those receiving enzalutamide (P=0.009), reported Alicia Morgans, MD, MPH, of the Dana-Farber Cancer Institute and Harvard Medical School in Boston.2
I’m a member of an online support forum for advanced prostate cancer on HealthUnlocked, and one of the common themes of other patients who have been on Xtandi® (enzalutamide) is significant “brain fog.” Many had such severe side effects that they stopped taking Xtandi® (enzalutamide), with one patient calling it “poison.”
Now, I take what’s said in forums like that with more than a grain of salt. There’s definitely some selection bias going on—patients who are having difficulties with their treatments are more likely to talk about them in a forum than those whose treatments are going well. We just don’t know how many are out there who have minimal side effects and tolerate the treatments well.
Drug Interactions
I surprise medical professionals when they ask me to list my current prescriptions because I only have one: amlodipine to manage hypertension. I checked on Drugs.com to see if any of the four drugs above will interact with the amlodipine:
Because a well-known side effect of ADT is osteoporosis/bone density loss, patients are usually given calcium and vitamin D supplements to slow or minimize the loss. Interactions with calcium and vitamin D:
Clearly, we’re going to have to have a discussion about the amlodipine before starting anything because it has made a difference. My systolic number has dropped by 33 points and my diastolic number has dropped by 24 points. Part of that may be the amlodipine, and part may be the fact that I’ve lost 44 lbs. / 20 kg since starting the amlodipine (or both).
Timing of Starting ADT + ARPI Therapy
You may recall back in April, I shared an AnCan Foundation video of a seminar featuring Dr. Ravi Madan and Dr. Melissa Abel from the National Cancer Institute (NCI). In it, they raise the notion that with new PSMA PET scans, we may be moving too quickly to treat biochemically recurrent prostate cancer and may be overtreating patients, subjecting them to the side effects of ADT either unnecessarily or prematurely.
From the video notes:
Dr. Paul Schellhammer, said in the meeting, ‘it’s like listening 15 years ago to the folks who began to promote active surveillance (in first line treatment).” Dr. Madan and Dr. Abel have collected solid data from around 150 patients that suggests men with slow PSA doubling times can “play the long game” as Dr. Ravi calls it, and defer active treatment when their disease recurs.
Just like the concept of active surveillance, this approach does seem counterintuitive. It’s a novel take that probably isn’t that widely accepted yet, but when you watch the video and look at the data, it makes sense. They’re not saying that treatment won’t be required at some point; they’re just making a case for delaying the treatment in order to maintain quality of life, especially if nothing is showing up on scans.
One difference in their approach is that they define a high risk PSA doubling time to be in the three to six month range, instead of the widely accepted less than nine month range.
I have to admit that the NCI doctors have me thinking more and more about the timing of starting this combination therapy because, let’s face it, no one leaps at the opportunity to go on hormone therapy given the “fun” side effects that it brings.
When I was on Eligard® (leuprolide acetate) during my salvage radiation therapy, I tolerated it probably better than most men do. I had mild to moderate fatigue; was more emotional; lost most of my libido; but avoided hot flashes, weight gain, and some of the other common side effects. The unknown is adding the ARPI to the mix.
Of the three ARPI agents available, Xtandi® (enzalutamide) seems to be the worst when it comes to side effects and patient experiences relayed in the prostate cancer forum. Of course, that’s the ARPI that the VA apparently uses in its treatment. NUBEQA® (darolutamide) seems to have the similar results when it comes to delaying metastasis with fewer side effects,3 so you can bet I’ll be having a conversation about this option with the medical oncologist when the time comes.
If you were to ask me right now what I plan on doing, my short answer is, “I don’t know.”
On the one hand, my PSADT hovering right around the action point and has been for some time now. Is that alone reason to act?
In his video, Dr. Madan basically concluded that, if your PSADT is >6 months and you don’t have any cancer showing up on scans, you can just continue to monitor the PSA without starting the hormone therapy—in other words, active surveillance for biochemical recurrence. As I recall, he observed patients for several years with increasing PSAs and consistently negative scans. Do I roll the dice based on his research and conclusions?
That’s one of the reasons that I want to have at least one more scan before committing one way or the other.
Once again, I’m in yet another decision dilemma with the science pulling in different directions.
Depending on what the VA MO says, I may also solicit the input of the UCSD MO one more time and go from there. I’m also open to thoughts and experiences from you.
More to come, that’s for sure.
Be well!
Arlen PM, Bianco F, Dahut WL, D’Amico A, Figg WD, Freedland SJ, Gulley JL, Kantoff PW, Kattan MW, Lee A, Regan MM, Sartor O; Prostate Specific Antigen Working Group. Prostate Specific Antigen Working Group guidelines on prostate specific antigen doubling time. J Urol. 2008 Jun;179(6):2181-5; discussion 2185-6. doi: 10.1016/j.juro.2008.01.099. Epub 2008 Apr 18. PMID: 18423743; PMCID: PMC2667701. ↩︎
November will mark the 16-year mark since my diagnosis with prostate cancer, and I’ve been riding that roller coaster ever since. Despite a radical prostatectomy (surgery) and salvage radiation therapy with concurrent androgen deprivation (hormone) therapy, it’s hanging on and continues to do its thing.
When I was diagnosed, I was completely oblivious to anything about prostate cancer, and I scrambled to get as smart as I could as quickly as I could so that I could make informed, researched treatment decisions.
The best time to learn about prostate cancer is before you are diagnosed with prostate cancer. That’s where Prostate Cancer Awareness Month comes into play.
Prostate Cancer Facts
Prostate cancer often has no symptoms (I was asymptomatic).
1 in 8 men in the U.S. will be diagnosed with prostate cancer.
1 in 6 black men will be diagnosed with prostate cancer.
In 2025, there were 313,780 cases, or one every two minutes.
There were 35,770 deaths, or one death every 15 minutes in 2025.
A simple prostate specific antigen (PSA) blood test can give an early warning to the possible presence of prostate cancer.
You don’t have to become a prostate cancer scholar, but it would be worth an hour or so to learn about the disease, how it progresses, and the various treatment options that are available. With luck, you’ll never have to put that education to use but, if you do, you’ll have a head start.