My most recent PSA results (3.32 ng/mL) have been weighing on me more heavily than I anticipated.
It’s not really the number that bothers me—I knew that it would increase. It’s what to do about that number that has had my mind in overdrive. In many ways, I feel as though I’m back to the weeks after the initial diagnosis sixteen years ago. Hours spent researching. Conflicting approaches to treatment options. Fuzzy definitions and guidelines. Frustration.
The real frustration for me is that none of my numbers or test results fit neatly into any of the guidelines, making decisions for such an important, potentially life-altering treatment even more challenging.
Cancer Staging
I know in the grand scheme of things, this matters very little, but I get frustrated by the inability of the prostate cancer community to clearly define what metastatic prostate cancer is. I’ve asked my medical team multiple times whether my cancer is metastatic, and each time I get a fairly squishy response.
It’s interesting that cancer in the pelvic lymph nodes, N1 using the TNM staging guidelines,1 is classified as Stage IV cancer, yet so many prostate cancer medical professionals say that disease confined to the pelvis really isn’t metastatic disease. Once the cancer is seen beyond the pelvic region, then they classify it as metastatic. Even my own doctors have said as much, and even the FDA thinks cancer in the pelvic region is metastatic and allows the use of ADT + ARPI drugs to treat it.
Of course, then you get to throw in the concept of micrometastases, and that isn’t covered anywhere in the staging guidelines. Yes, your PSA is rising indicating that there’s cancer somewhere, but we just don’t know where. That makes me wonder, if N1 disease in the regional lymph nodes is classified as Stage IV in the TNM guidelines, does that mean that micrometastatic disease should also be classified as Stage IV?
Rather than settling for the, “Kind of, sort of, maybe,” response, my black-and-white thinking mind goes back to the fundamental definition of metastasis:
Metastasis: The spread of cancer cells from the place where they first formed to another part of the body. In metastasis, cancer cells break away from the original (primary) tumor, travel through the blood or lymph system, and form a new tumor in other organs or tissues of the body. The new, metastatic tumor is the same type of cancer as the primary tumor.2
My prostate is gone. The cancer remains elsewhere. Therefore, by definition, I have metastatic prostate cancer. Simple concept for a simple mind.
Again, in the grand scheme of things, I suppose that the classification really doesn’t matter. If someone asks about my status, it’s just easier—and more easily understood—to say, “It’s progressed to Stage IV metastatic cancer,” instead of saying, “Do you have a few hours? It’s complicated.”
PSA Doubling Time
PSA doubling time (PSADT) seems to be an important data point in the decision-making process right now, but even with PSADT, there are disparate views on when to take action.
I’ve seen folks say that you don’t have to act unless your PSADT is less than six months. Others say less than nine months, and yet others say twelve months. If you’ve been following along, you already know that my PSADT has been hovering right around the nine month mark.
Depending on which guideline is used, I’m either late, early, or on the fence when it comes to starting systemic therapy. (And by systemic therapy, I’m talking androgen deprivation therapy with androgen receptor pathway inhibitors (ADT + ARPI).)
Imaging
Having a positive imaging result would certainly drive me to action. But with four 68Ga-PSMA-11 PET scans and one [F18] FDG PET scan not showing any regional or distant metastases, that would suggest that I could tap on the systemic therapy brakes for a while and wait until something does show up, even as my PSA continues to increase.
Balancing it All
So it really comes down to two factors in my mind, and I don’t know which carries more weight in the decision-making process.
Does my PSADT dipping below the nine month threshold carry more weight than negative imaging results and drive me to start systemic therapy? Or do the negative imaging results carry more weight than the PSADT and have me delay starting systemic therapy?
That’s what’s keeping me awake at night. Literally.
Medical Oncologist
I did email my VA medical oncologist (MO) last week after getting my PSA results. In essence, I asked if the jump in my PSA from 2.65 ng/mL to 3.32 ng/mL warranted a change in our plan to have the CT scan and bone scan, and to meet in early December.
In a nutshell, he described the increase as “mild,” and was okay with waiting to meet until December. He also said we could meet earlier if I wanted to.
I’m still processing whether I want to wait or have a conversation sooner. I’ve also thought of reaching out to the UCSD MO as well, and seeking his input on my increase in PSA.
[Actually, in writing this post, distilling how to weigh the two options was a lightbulb 💡 moment for me. I was having difficulty quantifying the problem until writing that a few moments ago, and that’s something to ask both of them.]
Summary
Once again, the act of writing has helped me coalesce my thoughts and ideas, which is good because it was a rough, emotionally draining week for me. Just as I said at the beginning of this adventure, you can research until the cows come home and drive yourself nuts in the process with all the contradictory guidance out there.
Even so, I’m glad I’ve done my homework over that last week or so because I’m much smarter about ADT + ARPI than I was, and that will help me with my discussions with the MO. I know it will happen at some point; it’s just a matter of when.
Time to step away from the computer into our 103° F / 39° C day. Ugh. 🥵
Be well!
Header image:Fishing boats, San Diego Harbor, California
I overachieved on this post. Normally, reporting PSA results would be quite simple and short. Not this time. The act of writing helps me organize my research and rationalize treatment decisions. Thanks for your indulgence!
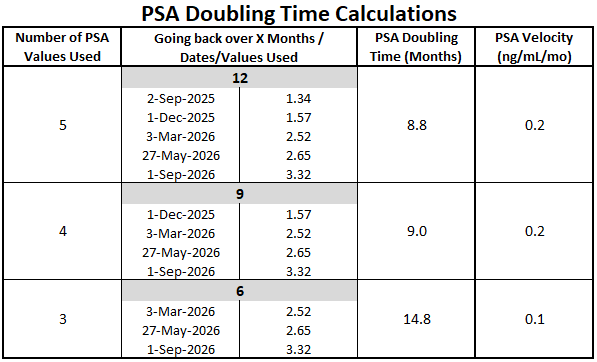
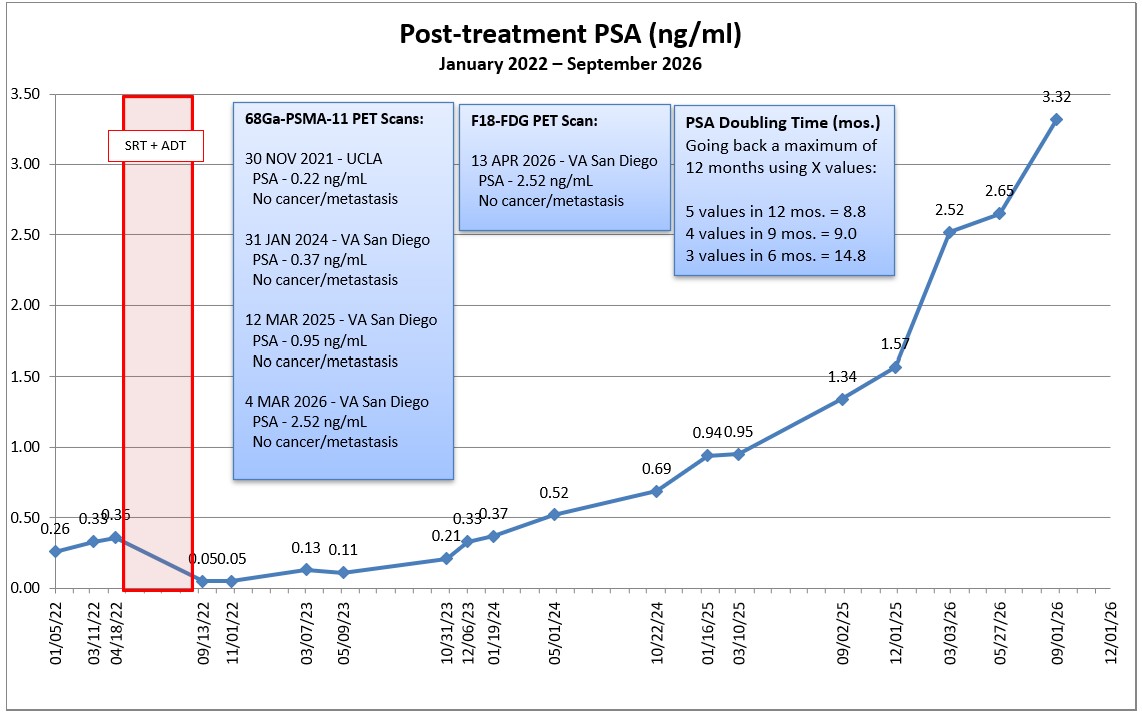
I went for my PSA test this morning, 1 September, and it was 3.32 ng/mL, up from 2.65 ng/mL back in May.
I expected my PSA to go up, and I guessed it would be around 3.0 ng/mL, so the amount it went up was a bit of a surprise. It’s closing in on my PSA level at initial diagnosis, 5.0 ng/mL.
PSA Doubling Time
Seeing as both the VA and UCSD medical oncologists (MO) stressed the importance of using PSA doubling time (PSADT) to guide treatment decisions during my meetings with them in June, I really wanted to try to nail down how it should be calculated.
The Memorial Sloan-Kettering PSADT Calculator is a great tool that I’ve been using, but it doesn’t provide any guidance on how many data points should be used over what period of time. I finally found some definitive guidance:
PSA values need not be consecutively rising and all values obtained over a maximum period of 12 months should be included in the calculation. The maximum period of the past 12 months is recommended to reflect the patient’s current disease activity, since in some men PSADT may change over time. Minimum requirements for the calculation are 3 PSA values obtained over 3 months with a minimum of 4 weeks between measurements.1
You can see that I’m sitting right around that nine-month PSADT point that’s the suggested trigger for action. I’m going to keep my mouth shut and ask my MO to calculate the PSADT and see what number they come up with.
Obviously, I’m concerned, but not panicked by this jump in my PSA. I’ll email the MO to see if we should stick to the current plan of having a CT scan on 23 November, or move it to an earlier date. Or to have another PSMA PET scan. In my mind, I’d like to have at least one more scan to try and see if we can determine what we’re dealing with before leaping into combination hormone therapy.
Combination Therapy
The MO’s were really encouraging action if my PSADT was nine months or less because, with faster doubling times, there is high risk of metastasis and prostate cancer-specific mortality. The action that they’re recommending is intermittent combination therapy using androgen deprivation therapy (ADT) plus an androgen receptor pathway inhibitor (ARPI). The specific drugs they’re recommending are Eligard® (leuprolide acetate) (ADT) and Xtandi® (enzalutamide) (ARPI). The Eligard® would stop the production of testosterone, and the Xtandi® would block the cancer cells from absorbing testosterone.
The reason that the MOs want to use the combination therapy is because of the results that were shown in the EMBARK trial. Using Eligard® and Xtandi® together had 87.3% of patients in the trial reach the five-year point metastasis-free. Using just Eligard® alone—the old standard of care—just 71.4% of patients were metastasis-free at five years. The combination therapy won’t prevent progression to metastasis; it just slows it down. This short (2 min.) video from the New England Journal of Medicine gives a good overview:
The combination therapy would be given intermittently, with nine months on the medication and, if my PSA drops to a certain level (usually below 0.2 ng/mL) and stays there, there wouldn’t be a need to restart the combination therapy until there’s a rise in my PSA.
The one thing that I couldn’t find or confirm in my research was if there was a specific PSA level where, if you exceed it, this combination therapy should be started. The UCSD MO seemed okay with waiting until it was as high as 5 to 10 ng/mL if the PSADT didn’t indicate high risk.
Xtandi® (enzalutamide) is just one of several drugs known as Androgen Receptor Pathway Inhibitors (ARPIs). Two others that are commonly used include ERLEADA® (apalutamide) and NUBEQA® (darolutamide). Each has its own similar, but slightly different side effects.
Side Effects / Adverse Events
Messing around with your hormones can have substantial and sometimes debilitating side effects and, when using combination therapy, they can be additive. The National Cancer Institute has defined five grades of adverse events based on their severity:
Grade
Impact
Grade 1
Mild; asymptomatic or mild symptoms; clinical or diagnostic observations only; intervention not indicated.
Grade 2
Moderate; minimal, local or noninvasive intervention indicated; limiting instrumental ADL or mild/moderate impact on age appropriate normal daily activity (pediatric)*.
Grade 3
Severe or medically significant but not immediately life threatening; hospitalization or prolongation of hospitalization indicated; disabling; limiting self-care ADL or severe impact on age appropriate normal daily activity (pediatric)**
Activities of Daily Living (ADL): *Instrumental ADL refers to preparing meals, shopping for groceries or clothes, using the telephone, managing money, etc. **Self-care ADL refers to bathing, dressing and undressing, feeding self, using the toilet, taking medications.
Clearly, a patient would want to steer clear of any Grade 3 or 4 side effects if possible. When you look at the grades of adverse events in the summaries of each of the drugs below, you’ll see that the percentages of patients experiencing an adverse event at all grade levels can be quite high in some cases. Bottom line: ADT + ARPI will adversely impact you and your quality of life in some shape or form. It’s just a matter of degrees.
Some of the possible, more severe side effects include:
Heart disease, stroke, or mini-stroke
Fractures and falls
Lung problems
Seizures
Severe skin reactions
And you can see what percent of the time that patients experienced some of these side effects by adverse event grade in section 6.1 of the prescribing information HERE or in these tables HERE. Some of the Grade 3 or 4 adverse events occurred as much as 8% of the time.
Some of the possible, more severe side effects include:
Heart Disease
Seizure
And you can see what percent of the time that patients experienced some of these side effects by adverse event grade in section 6.1 of the prescribing information HERE. Some of the Grade 3 or 4 adverse events occurred as much as 4% of the time.
Some of the possible, more severe side effects include:
Seizure
Posterior Reversible Encephalopathy Syndrome (PRES) (Involves the brain with seizure or quickly worsening symptoms such as headache, decreased alertness, confusion, reduced eyesight, blurred vision or other visual problems)
Allergic reactions
Heart disease
Falls and bone fractures
Swallowing problems or choking (because of the size of the pills)
And you can see what percent of the time that patients experienced some of these side effects by adverse event grade in section 6.1 of the prescribing information HERE. Some of the Grade 3 or 4 adverse events occurred as much as 9% of the time.
Some of the possible, more severe side effects include:
Heart attack
Elevated blood sugar and increased risk of developing diabetes
Convulsions
And you can see what percent of the time that patients experienced some of these side effects by adverse event grade in section 6.1 of the prescribing information HERE.
Anecdotal Side Effect Experiences
One of the side effects that isn’t specifically mentioned above was cognitive decline. In a study, it was shown:
Patients with advanced prostate cancer treated with enzalutamide (Xtandi) had a significantly greater decline in cognitive function compared with those who received darolutamide (Nubeqa), according to results from a phase II trial.
Median cognitive change in the maximally changed cognitive domain (MCCD) from baseline to 24 weeks was -15.8% for those receiving darolutamide versus -36.1% for those receiving enzalutamide (P=0.009), reported Alicia Morgans, MD, MPH, of the Dana-Farber Cancer Institute and Harvard Medical School in Boston.2
I’m a member of an online support forum for advanced prostate cancer on HealthUnlocked, and one of the common themes of other patients who have been on Xtandi® (enzalutamide) is significant “brain fog.” Many had such severe side effects that they stopped taking Xtandi® (enzalutamide), with one patient calling it “poison.”
Now, I take what’s said in forums like that with more than a grain of salt. There’s definitely some selection bias going on—patients who are having difficulties with their treatments are more likely to talk about them in a forum than those whose treatments are going well. We just don’t know how many are out there who have minimal side effects and tolerate the treatments well.
Drug Interactions
I surprise medical professionals when they ask me to list my current prescriptions because I only have one: amlodipine to manage hypertension. I checked on Drugs.com to see if any of the four drugs above will interact with the amlodipine:
Because a well-known side effect of ADT is osteoporosis/bone density loss, patients are usually given calcium and vitamin D supplements to slow or minimize the loss. Interactions with calcium and vitamin D:
Clearly, we’re going to have to have a discussion about the amlodipine before starting anything because it has made a difference. My systolic number has dropped by 33 points and my diastolic number has dropped by 24 points. Part of that may be the amlodipine, and part may be the fact that I’ve lost 44 lbs. / 20 kg since starting the amlodipine (or both).
Timing of Starting ADT + ARPI Therapy
You may recall back in April, I shared an AnCan Foundation video of a seminar featuring Dr. Ravi Madan and Dr. Melissa Abel from the National Cancer Institute (NCI). In it, they raise the notion that with new PSMA PET scans, we may be moving too quickly to treat biochemically recurrent prostate cancer and may be overtreating patients, subjecting them to the side effects of ADT either unnecessarily or prematurely.
From the video notes:
Dr. Paul Schellhammer, said in the meeting, ‘it’s like listening 15 years ago to the folks who began to promote active surveillance (in first line treatment).” Dr. Madan and Dr. Abel have collected solid data from around 150 patients that suggests men with slow PSA doubling times can “play the long game” as Dr. Ravi calls it, and defer active treatment when their disease recurs.
Just like the concept of active surveillance, this approach does seem counterintuitive. It’s a novel take that probably isn’t that widely accepted yet, but when you watch the video and look at the data, it makes sense. They’re not saying that treatment won’t be required at some point; they’re just making a case for delaying the treatment in order to maintain quality of life, especially if nothing is showing up on scans.
One difference in their approach is that they define a high risk PSA doubling time to be in the three to six month range, instead of the widely accepted less than nine month range.
I have to admit that the NCI doctors have me thinking more and more about the timing of starting this combination therapy because, let’s face it, no one leaps at the opportunity to go on hormone therapy given the “fun” side effects that it brings.
When I was on Eligard® (leuprolide acetate) during my salvage radiation therapy, I tolerated it probably better than most men do. I had mild to moderate fatigue; was more emotional; lost most of my libido; but avoided hot flashes, weight gain, and some of the other common side effects. The unknown is adding the ARPI to the mix.
Of the three ARPI agents available, Xtandi® (enzalutamide) seems to be the worst when it comes to side effects and patient experiences relayed in the prostate cancer forum. Of course, that’s the ARPI that the VA apparently uses in its treatment. NUBEQA® (darolutamide) seems to have the similar results when it comes to delaying metastasis with fewer side effects,3 so you can bet I’ll be having a conversation about this option with the medical oncologist when the time comes.
If you were to ask me right now what I plan on doing, my short answer is, “I don’t know.”
On the one hand, my PSADT hovering right around the action point and has been for some time now. Is that alone reason to act?
In his video, Dr. Madan basically concluded that, if your PSADT is >6 months and you don’t have any cancer showing up on scans, you can just continue to monitor the PSA without starting the hormone therapy—in other words, active surveillance for biochemical recurrence. As I recall, he observed patients for several years with increasing PSAs and consistently negative scans. Do I roll the dice based on his research and conclusions?
That’s one of the reasons that I want to have at least one more scan before committing one way or the other.
Once again, I’m in yet another decision dilemma with the science pulling in different directions.
Depending on what the VA MO says, I may also solicit the input of the UCSD MO one more time and go from there. I’m also open to thoughts and experiences from you.
More to come, that’s for sure.
Be well!
Arlen PM, Bianco F, Dahut WL, D’Amico A, Figg WD, Freedland SJ, Gulley JL, Kantoff PW, Kattan MW, Lee A, Regan MM, Sartor O; Prostate Specific Antigen Working Group. Prostate Specific Antigen Working Group guidelines on prostate specific antigen doubling time. J Urol. 2008 Jun;179(6):2181-5; discussion 2185-6. doi: 10.1016/j.juro.2008.01.099. Epub 2008 Apr 18. PMID: 18423743; PMCID: PMC2667701. ↩︎
Before getting into the conversation with the urologist, I went for my bone density scan last week. The results? I have bones. They’re dense (i.e., normal). Now we have a baseline for future reference for if and when I start down the hormone therapy path.
Yesterday’s meeting with the urologist was unusually animated, if not bordering on contentious. The appointment was late in the afternoon (around 3:45 p.m. when she arrived), so perhaps she had had a crappy day and was ready for it to end.
I tried explaining my conversations with both oncologists, and she kept interrupting, sometimes with questions that made it seem that she wasn’t paying much attention. (She was on her computer reviewing my file as I talked; usually she’ll have reviewed the file before even walking into the exam room.)
At one point she said, “You have three cooks in the kitchen and should probably stick with one,” referring to the fact that I had two oncologists and her trying to manage my case.
When it comes to treatment, she’s still of the opinion to wait until metastasis to start hormone therapy, mainly because of the associated side effects and possible earlier resistance to the therapy. I mentioned that both oncologists recommended intermittent hormone therapy, and she seemed puzzled by that for some unknown reason.
I mentioned that the plan was for me to have another PSA test in the first week of September and, if warranted, a CT scan and bone scan in December. She seemed indifferent and offered no comment one way or the other.
By the end of the appointment, it was pretty clear that she was of the mindset that there’s little that she as a urologist can do at this point in my case management, and that the ball belongs squarely in the court of the oncologists. I agree. She did say, though, that if I start to have urinary symptoms that may be from the radiation or surgery (e.g., strictures, worsening incontinence), to come back to Urology for investigation and possible treatment. We did not set up a follow-up appointment for Urology.
Back in April, the oncologist suggested they take the lead on my case and, after yesterday’s appointment with the urologist, it’s clear that that’s what needs to happen.
I’ve got the PSA test on my calendar on 2 September. We’ll get the results, calculate PSA doubling time, and consult with the oncologists to determine the next steps based on the results.
If my PSA shoots up again like it did between December and March, reducing my PSA DT, I might be more inclined to act. But if it continues on a flatter trend like it did between March and May, I’d be inclined to kick the can down the road another three months.
So I’ll continue to live life in three-month increments until the results tell me it’s time to do something. Good thing I have a lot of hurry-up-and-wait experience from the Navy. 🙂
My visits with the medical oncologists yesterday and today went well, and there was some consensus on how to proceed.
[BLUF: We’re kicking the can down the road three months.]
UCSD Oncologist
The first part of the meeting was getting the doctor up to speed on my case, as he didn’t have any of the history. Of course, nerd me came prepared with a two-page Reader’s Digest chronological summary of my diagnosis and treatment, printouts of my PSA charts, and copies of the PSA doubling time (PSA DT) calculations.
PSA Doubling Time
Because PSA DT is an important number in the decision-making process, I opened the conversation by asking him how many data points should be used in the calculations. He chuckled a bit before saying that one of the downfalls of using PSA DT is you can pick and choose the data that you want to get the answer that you want. So true.
I calculated my PSA DT using 3, 4, and 5 values and came up with different answers:
Number of values used
Going back X months
Calculated PSA DT
3
6
7.6 months
4
9
8.0 months
5
14
9.2 months
He just looked at the curve on my PSA tracking chart and estimated in his head that it was around nine months. In his eyes, that six to nine month PSA DT warrants closer observation and monitoring.
Inconclusive PSMA PET scans
We discussed my four inconclusive PSMA PET scans and [F18] FDG PET scan, and whether he thought that I was PSMA negative. He thought it was unlikely that I was, offering up a case with another patient whose PSA was over 50 ng/mL and still showing up negative on PSMA PET scans.
One of the reasons that we talked about that at some length was that he suggested that Pluvicto / Lutetium-177 might be an option.
I asked about getting an Axumin scan or a Choline-11 scan, and he wasn’t in favor of doing either of those at the moment.
When to Start ADT
We also discussed when to start androgen deprivation (hormone) therapy (ADT). He didn’t have a set of specific criteria that he would use—e.g., specific PSA number, evidence of metastasis—but did focus in on the rate of PSA rise (PSA DT) and “patient motivations and preferences.”
What type of ADT
The doctor was a proponent of intermittent therapy in my case with six to twelve months on, then a similar period off. His goal would be to “maximize time off treatment” as long as my PSA is holding relatively steady and not going bonkers.
He seemed a tad hesitant to start with the combination therapy of ADT + ARPI (Eligard + Enzalutamide), but wasn’t opposed to it, either. He wasn’t a fan of trying the Enzalutamide alone because of its side effects (gynecomastia, in particular) and not seeing any substantial changes in long term outcomes.
Summary
I did share with the doctor the VA MO’s desire to start ADT + ARPI sooner rather than later, and he had a much lower sense of urgency in taking action. And, while I was a bonehead and didn’t explicitly ask him for his recommended course of action, the entire conversation led me to conclude that his preference was for continued close observation.
VA Oncologist
I technically didn’t meet with the oncologist; I met with a nurse practitioner who had reviewed my case with the oncologist just before (and during) my appointment.
Discussion
It was interesting that she opened the conversation with a quick review of my last appointment there, told me my PSA results from last week, and then said something along the lines of, “If you’re not ready to start ADT today, the doctor is okay with monitoring for another three months.”
At that point, I mentioned that I went to the UCSD MO the day before, and I spent a good chunk of time relaying how that meeting went.
I reminded her that I have the bone density scan in a few weeks and I intended to go through with that to establish a baseline even though we might not start ADT right away. She agreed.
I’m still meeting with the VA urologist on 23 June and want to get their thoughts on what’s next.
Summary
We’re going to do another PSA test in September, and the VA MO didn’t want to schedule an appointment with me until December with another PSA test just before that meeting, too. Interestingly, the VA MO also wanted to schedule a regular CT scan and bone scan ahead of the December appointment.
However, if the September PSA test jumps up significantly, we’ll revisit that plan based on the results. That may change doing the CT/Bone scans to another PSMA PET scan.
The Plan
In short, we’re going to kick the can down the road another three months.
More specifically:
Bone density scan – 17 June
Urologist appointment – 23 June
PSA test – First week of September
CT and Bone scan – First week of December
PSA test – First week of December
VA Oncology Appointment – 8 December
Summary
On the whole, I’m pleased with the plan as it stands right now. The UCSD MO emphasized the shared decision-making approach, adding in his notes, “Daniel is very well educated about his illness and understands there is no clearcut right and wrong answer.” Ain’t that the truth (about the no right or wrong answer).
Once I cleared the hurdles of getting set up in the UCSD system, I was impressed by the friendliness and professionalism of their staff in the department. They have a patient portal app that allows access to records and makes communicating about appointments—in both directions—quite easy.
One thing that I’ve noticed with both the VA and UCSD oncology departments is that their empathy and caring nature seems to be a notch or two above that of their respective urology departments. Not that the urology teams aren’t caring or empathetic; it’s just that the oncology folks seem to take it a step further.
I know the VA MO expressed a desire to take the lead on my case at my last appointment, and I’ll mention that to the urologist on the 23rd. And, for now, as pleasant as the experience at UCSD was, I plan on having the VA be my primary source of care.
I went for my PSA test this morning and already have the results this afternoon (a pleasant surprise).
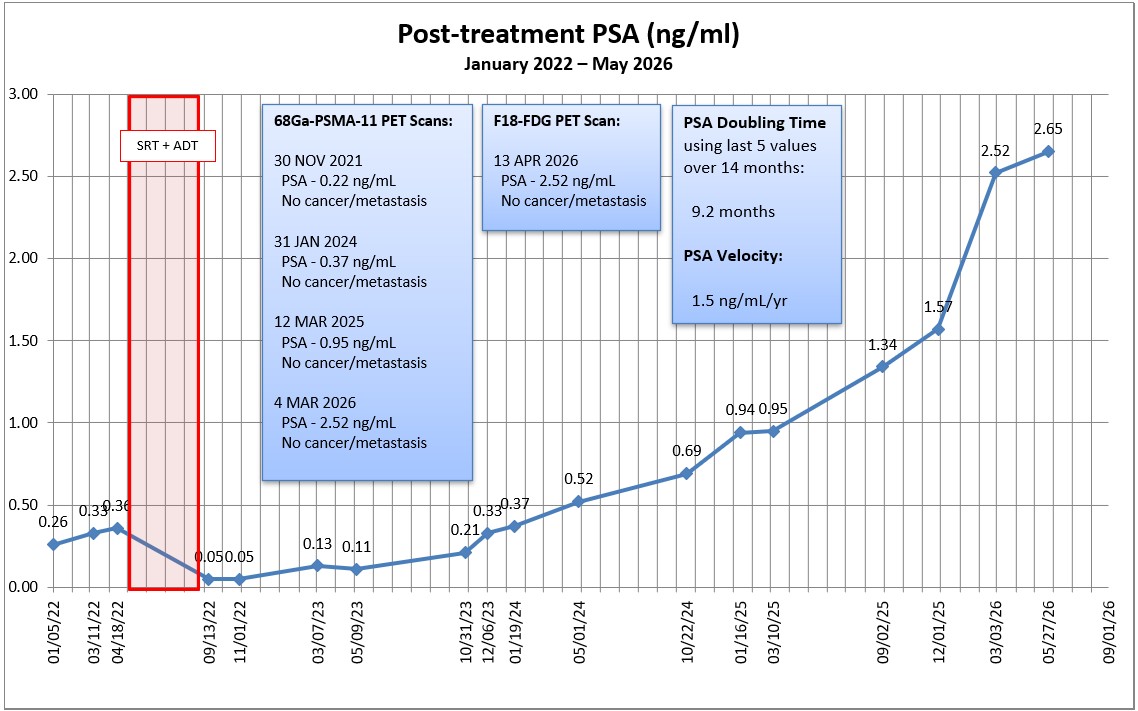
My PSA increased, but not as much as I expected it to. It went from 2.52 ng/mL in March to 2.65 ng/mL today.
If I use the last five PSA values to calculate PSA doubling time going back 14 months, my PSA DT is 9.2 months. If I use the last four PSA values going back only nine months, it’s 8.0 months. Again, the VA medical oncologist used the nine month PSA DT one of the triggers to start hormone therapy.
Armed with these latest results, I should be ready for my upcoming appointments:
Monday, 1 June – UCSD Medical oncologist
Tuesday, 2 June – VA Medical oncologist
Wednesday, 17 June – Bone density scan to establish baseline
Tuesday, 23 June – VA Urologist
I definitely plan on asking the UCSD MO what his thoughts are on an Axumin scan, and whether it’s worth pursuing before we start hormone therapy. If he agrees, I’ll have to add that to the schedule, too.
I also had another testosterone test done to establish a baseline should I opt to start hormone therapy. It came in at 416 ng/dL (reference range 200-800 ng/dL).
Over the holiday weekend, UCSD sent an automated email asking me to complete their electronic check-in process. Sheesh. It took more than an hour of filling out forms, providing history, and updating insurance. The only thing they didn’t ask for was our family cat’s name from when I was five years old. Hopefully, getting all that taken care of in advance makes the appointment go more smoothly.
We last left our hero with the beginning of a head cold after his scan and oncologist meeting. And, boy, what a head cold that turned out to be.
Normally, a typical head cold lasts a week or so and you’re back to normal. Not this time. This was the most stubborn virus, hanging on for three weeks and change. It was ugly. So ugly, in fact, that I went to the doctor for help.
The cold started out with a light fever and lots and lots of coughing. Of course, when you have your prostate plucked from your pelvis and they zap what’s left, stress incontinence is an issue. If I have a light cough, I’m generally okay, but with this virus, I was having deep coughs where it seemed as though I was trying to turn my lungs inside out. I had to switch to the heavy-duty incontinence pads and, even then, I blew out two of them with coughing fits, leaking into my underwear and jeans. Messy and not fun.
The doctor gave me something to calm the dry coughs, and that had a bit of a positive effect. But then my sinuses filled, my nose was running, and I was coughing up phlegm so I switched to something else to deal with that.
Long story shorter, it’s pretty much all behind me now, and that’s a good thing. Maybe I’ll go back to the COVID days and wear masks when riding packed transit or wandering the halls of hospitals.
While I was down for the count, I had plenty of time to dig into more about androgen deprivation therapy (ADT), its pros and cons, and the timing of starting it. Sadly, I could find information that supported pretty much any perspective you wanted, which really isn’t all that helpful.
On the whole, it appears the current thinking is to start ADT sooner rather than later, and to use a doublet therapy, i.e., ADT + ARPI. This seems to delay time to metastasis, but has the obvious cost of substantial side effects.
On a related note, I called UCSD on 30 April to set up a second opinion appointment with the medical oncologist that’s well-respected and that the VA called to consult on my case two years ago. Because I was already in their system, that helped a little. I had to update my insurance information, and they said they’d get back to me in 2-3 business days. They didn’t, so I called back today, 11 May. They put me on the “high priority” call-back list this afternoon to be called back “between now and 48 hours.” Okie-dokie. And they say scheduling appointments at the VA is difficult…
I’ve got a number of appointments coming up at the end of May and into June:
27 May – PSA Test and other pre-ADT labs ordered by the oncologist
2 June – Meeting with VA medical oncologist
17 June – Dexa Scan bone density scan for baseline
23 June – Meeting with VA urologist
With luck, I’ll be able to add the UCSD medical oncologist to that list as well.
I really want the PSA test results—specifically, the PSA doubling time—to be a guide into what happens next and when.
One of the other things that I dug into a bit when I was down with the cold was how many values to use when calculating PSADT. As expected, there were dozens of different answers. Grr. My pea-sized engineer’s brain decided that I’ll use the last four PSA values if they cover at least a year. To me, that would render more useful information that shows the latest trend versus loading in all data points that may skew the results to show something less aggressive. But what do I know?
Using the Memorial Sloan-Kettering PSADT calculator and four data points over the last year, my PSADT is 8.9 months. Using a second calculator I found, it’s 8.21 months. For grins and giggles, I plugged in the last two years worth of data, and my PSADT was 10.4 months. Doing my research on ADT, PSADTs in the 6-9 month range seemed to be a trigger for action.
My PSA in March was 2.52 ng/mL, and I suspect it will be approaching 3.0 ng/mL at the end of May.
Obviously, this summer will be a series of data collection, evaluation, and big decision-making. Yippee! <sarcasm font>
It’s been a busy two days hanging out at the doctor’s offices between the scan and the oncologist. Here’s a summary of each, my final thoughts, and a quick explainer about hormone therapy for the uninitiated at the end.
18F-FDG PET Scan
“No evidence of metabolically active malignancy or metastatic disease.”
Well, I hate to say it, but I’m not necessarily surprised by that result. I didn’t have high hopes of getting a definitive answer going into the scan given its lower sensitivity and lower specificity, but I thought it was definitely worth the effort.
As far as the procedure itself was concerned, it was slightly different than the 68Ga-PSMA-11 PET scan. I had to fast for at least 6 hours (no food, just water) before the injection of the 18F-FDG tracer. They also had to measure my blood glucose level to ensure it was under 200 mg/dL (it was). If it was over, the scan would have been canceled.
There was a one-hour waiting period for the tracer to distribute through my body, and the scan itself took 45 minutes. Seeing as I had to get up at 4:30 a.m. for my 7 a.m. appointment, that hour in the recliner was much needed.
Oncologist
I actually met with two medical oncologists this morning, the resident about to complete his training (MO Jr.) and the full-blown MO Sr. who focuses on prostate and breast cancer. It was a good, nearly hour-long discussion. In a nutshell:
It was disappointing that the imaging didn’t show anything and, even though it would be nice to know where the cancer is located, MO Sr. felt it was time to start systemic treatment.
MO Sr.’s triggers for starting hormone therapy were a PSA greater than 2.0 ng/mL (I’m at 2.52) and a PSA doubling time less than 9 months (I’m at 8.9 months).
MO Sr. said that, with my numbers, I’m at “higher risk” for this to get away from us and metastasize.
MO Jr. said that the window for curative options has closed and that treatment going forward would be “palliative.” (I already knew that curative options were out the window.)
Both agreed it’s time for them (Oncology) to take the lead on my case at this point, with Urology still available in a supporting role.
Both suggested dual therapy involving androgen deprivation therapy (ADT) using Eligard (leuprolide acetate) and and androgen receptor pathway inhibitor (ARPI) using Xtandi (enzalutamide) as the current standard of care. [See explanation below if you’re unfamiliar.]
MO Sr. also suggested intermittent therapy over continuous therapy, using a 9-month schedule to start.
If she had her way, I believe MO Sr. would have had me start the therapy in the next week or so. I tapped on the brakes on that idea. I told her that Urology wanted another PSA test done in early June, and I thought it would be good to get that done before starting anything. Also, I’m traveling in May and I simply wanted to postpone anything until after I return. Six weeks won’t make that much of a difference.
We agreed, in concept, to the following:
No more scans to try to located the cancer for now.
Get pre-therapy lab work done the week after Memorial Day to establish baseline testosterone and PSA levels (among others) ahead of therapy.
Get a Dexa bone density scan to get a baseline prior to starting treatment (extended ADT can weaken bone density).
Meet on 2 June to review the results and make the final decision as to whether to start treatment.
Final Thoughts
It’s only been a few hours since the meeting, and I’m still trying to absorb it all and process it. Of course, after 15+ years of dealing with this, I knew we would eventually get to this point. Am I ready or willing to take the advice of the National Cancer Institute doctors in the video I shared recently to just monitor and delay treatment? I don’t know. It’s something that I’ll have to contemplate over the next six weeks or so.
I will say that I was pretty impressed with the Oncology Department as a whole. You’re assigned a care coordinator and given their direct phone number for all questions or concerns, and both doctors were good at listening and engaging in a real conversation. It seemed like they were a bit more empathetic over all, and that’s a good thing.
Certainly a lot to take in in the days and weeks ahead. I’m open to thoughts and feedback.
Be well!
—Dan
Hormone Therapy Explained
For those who aren’t really familiar with how prostate cancer works and what role hormone therapy plays, here’s a grossly over-simplified explainer.
Prostate cancer feeds off of testosterone and, as long as there’s a supply of testosterone, the cancer will continue to grow.
There are two ways to deprive the cancer of testosterone. The first is to stop or slow the production of testosterone. The second is to block the cancer cells from receiving the testosterone. The current standard of care is to use both methods simultaneously.
Let’s say the cancer cells are in the bottom of your favorite travel mug, thirsty for testosterone. If you put the mug under running water from your tap, the cells get the water (testosterone) they need and the cancer grows. But if you turn the tap off, the water (testosterone) stops flowing, and the cells in the bottom of the mug can’t grow. This is called androgen deprivation therapy (ADT).
The other way to stop the cancer cells in the bottom of the mug from getting water (testosterone), is to simply put the lid on and block the water from entering the mug. This is called androgen receptor pathway inhibitors (ARPI).
If you do both simultaneously, you can really slow the growth of the cancer. But we also know that some taps have slow leaks that drip water and, if the lid is slightly open, water (testosterone) and still make it to the cancer cells inside the mug.
There are two ways of turning the tap off. One, an orchiectomy, is a radical, surgical and permanent removal of the testes. But the adrenal glands also produce a small amount of testosterone, too, so the flow isn’t completely stopped.
The other is to use an ADT drug to have the brain tell the testes to stop producing testosterone. The drug is given via an injection in typically one, three, or six month doses, and it has significant side effects: hot flashes, mood swings, fatigue, loss of libido, loss of muscle strength, and loss of bone density, to name a few.
The way to put a lid on the mug is through an ARPI drug that’s usually taken in pill form daily. In my case, MO Sr. was recommending Xtandi (enzalutamide) as the ARPI. It has its own host of side effects: muscle and joint pain, fatigue, falls and bone fractures, headaches, high blood pressure and others.
The good news is that this combined treatment option can keep the cancer at bay for years (as long as you stay on it for years). However, at some point, the cancer can become resistant to the drugs, and you may have to move to stronger treatment options like chemotherapy.
Again, this is an oversimplification for those new to the topic.
As soon as I hung up the phone with the doctor yesterday, I started memorializing our conversation in Google Keep while waiting for my turn in the barber’s chair, and that was the outline I used for last night’s post about the conversation.
As I said last night, I had planned on documenting the conversation in an email to the doctor this morning. I drafted what I thought was an accurate, reasoned response but, before I was going to send it, I wanted to see if I could get his take on the conversation in my patient notes. I logged onto the patient portal and found his notes from the conversation.
Apparently, the doctor and I have had a massive disconnect.
He mentioned our discussion about Axumin scans, saying, “that this is not recommended at this time given prior negative PSMA PET imaging and the limited likelihood that Axumin would provide additional clinically actionable information.”
He also referenced our discussion about Pylarify scans, saying, “he recently underwent PSMA PET and that repeat advanced imaging would not be expected to change immediate management. Will review timing/appropriateness of repeat PSMA-based imaging if PSA continues to rise.”
He closed his comments with a recommendation to see Hematology/Oncology.
It was like a sucker punch to the gut—I had a genuine physical reaction to reading his notes.
This tells me two things.
First, he is not convinced that there is such a thing as a PSMA-negative patient for whom PSMA PET scans won’t work. That view is reinforced by his comments yesterday that he was confident my cancer expresses PSMA. In his mind, the 68Ga-PSMA-11 PET scan is definitive in its findings.
Second, it tells me that he isn’t pursuing any alternate imaging at all. Just let my PSA continue to increase and try again with another PSMA PET scan.
Needless to say, I discarded my draft e-mail to him, stepped away for most of the day, and have just been trying to process how to proceed. Of course, I’ll re-write my email to him politely highlighting the disconnect between our versions of the conversation.
I wish I could understand his reluctance to believe that I may be PSMA-negative. A quick search last night gave me a handful of papers from reputable organizations on the topic:
Of course, there’s a lot of gobbledygook that goes way over my head in those papers, but the common theme is that PSMA-negative patients do exist and that affects imaging. They only possible distinction that I’ve come up with from briefly skimming those papers is that more aggressive cancers seem to express more PSMA than less aggressive cancers. Maybe the doctor could confirm that or educate me.
Of course, the Prostate Cancer Research Institute has a video on this very topic:
What’s next? I’m thinking that I’m going to pursue two parallel paths, one within the VA and one outside of it. Both will likely take weeks if not months to pursue. (I’m not panicking about this, but I also don’t want to keep kicking the can down the road without doing anything to guide our decision-making, especially seeing as my PSA doubling time seems to be shrinking.)
Within the VA, I’m going to:
Write the urologist and let him know that I came away from our phone call with a completely different take.
Push to get the appointment with Oncology and hope to enlist them as an ally in trying to get an alternate scan sooner rather than later. In the in-person meeting, the urologist seemed to be deferential to their opinion.
If neither of those result in any action, I’ll meet with the patient advocate at the VA and see if that can break the log jam either within the VA or by allowing me to gain community care outside of the VA.
Outside the VA, I’ll look at:
Identifying what’s needed to become a patient at UCSD. It may not require much, as they did my salvage radiation therapy almost four years ago.
Try to set up an appointment with the medical oncologist that the VA consulted when we talked two years ago.
Get his take on alternate imaging.
I will tread very carefully because I don’t want to screw up any eligibility for care within the VA by going outside the VA or create confusion as to who is really taking the lead on my care. That’s why it’s really best that, if the VA can’t or won’t pursue additional screening, that they are the ones who initiate the request for community care. It’s something I need to research.
So that’s how I’m going into the weekend. How about you?
Those of us of a certain age may remember the “Stump the Band” segment on the Johnny Carson show, where audience members asked the band to play some obscure song. Well, today was my turn at “Stump the Urologist.”
It was a very productive meeting that lasted nearly 40 minutes which was unusual. I came equipped with hard copies of my PSA chart, the MSKCC PSA doubling time (PSA-DT) calculator results, and my list of questions. He was impressed and really pleased with the chart in particular.
We started talking about how my four PSMA PET scans were all inconclusive, and I steered the conversation to whether I might be one of the 10% for whom PSMA PET scans don’t work. He seemed to be a bit skeptical at first, but he also said it was a possibility.
Given that my PSA increased substantially and my PSA-DT was decreasing, I wondered if it would be better to jump into ADT sooner or if there’s still value in trying to find the cancer’s location with imaging. He was of the opinion to continue to try to find it before starting ADT.
I had a series of questions that really dealt specifically with ADT, and he said it was a bit premature to think about those and that they would be better answered by a medical oncologist. I knew that I was jumping the gun with some of them, but I thought I’d ask anyway. During that part of the conversation, I did mention that I tolerated the ADT probably better than most when I had it for my salvage radiation therapy, but that I wasn’t eager to jump into it earlier than necessary.
After that, he took control of the conversation and asked me about my status when it came to sexual function and incontinence, and offered up options to deal with both if I was interested.
Then we returned to the topic of next steps, and that’s where I played “Stump the Urologist.” (Who, by the way, was a full-blown internist and not a resident.) He grabbed my PSA chart and excused himself for a few minutes as he went off to consult with the department head.
When he returned, I was a bit surprised when he put his faith in the results of the PSMA PET scan, saying it has the best sensitivity and the best specificity of any scan out there. He said that they had moved away from the Axumin scans because they were the old technology.
I politely pushed back, reminding him that a PSMA PET scan should have had an 80% – 90% chance of finding my cancer at my PSA level if I had the PSMA protein for the 68-Gallium tracer to lock onto. But if I don’t have that PSMA protein, the sensitivity and specificity of the scan won’t matter because nothing will ever light up. He really couldn’t argue against that.
I went back to the topic of ADT and mentioned that I met with a medical oncologist (MO) two years ago, and received conflicting opinions on when to start ADT. The MO said she would start my ADT when my PSA hit 2.0 ng/mL (a urologist said she wouldn’t start it until there was evidence of metastasis). Today’s urologist said he looks for one of three “triggers” to begin ADT: PSA > 10.0 ng/mL 😲; PSA-DT less than six months; or evidence of metastasis.
I also mentioned that the VA MO that I saw two years ago was a general oncologist and not someone who specialized in genitourinary cancers and, as helpful as she was, she had to consult with a UCSD MO who specifically deals with prostate cancer. I sowed the seed of eliminating the VA MO as a middleman if they have to consistently consult the UCSD doctor (who is highly regarded in the field), and suggested that I could just see him directly. I’m not sure if that will take root.
Finally, I did ask a very basic question given how elusive this has been: Is this even cancer? He said that, if I hadn’t had a prostatectomy, that there might be other explanations for the rising PSA. But he was confident that we are, in fact, dealing with cancer.
That led to a follow-up question of: Is it metastatic? Based on the information we have, he said it’s not. He seemed to squirm a bit when I asked about it being micro-metastatic, because, in his mind, that wasn’t very well-defined.
Before mapping out a plan, I have to admit that my ego puffed up a tad when he said, “You’re the best educated patient I’ve seen in weeks.” He also admitted that my case was a bit puzzling to them and not something they routinely see.
We agreed on three actions:
The doctor is going to explore how and where I can get an Axumin scan, and if the VA will authorize it if I have to go outside the VA. That may take a day or two to get an answer. I mentioned that I’d be willing to use Medicare and go out on my own if necessary.
He is doing a referral to get me seen by the VA oncology team to get them familiar with my case. I suspect it will take a few days to hear from the scheduler.
We do another PSA test in June and meet to see where we’re at.
All in all, this was a good meeting with a robust discussion about my case that has all of us scratching our heads as to what’s going on and what to do next. Frustrating? Yes, to a degree. But, as we discussed during the meeting, nothing is black-and-white in the world of prostate cancer.
More to come.
Be well!
For my readers outside the U.S. who may not be familiar with Johnny Carson, I was going to link a random video clip of his “Stump the Band” segment above and, when I searched YouTube, this—of all clips—was the one that popped up first. I think you’ll see the related humor in it once you watch it. 😂
Header image:Anza-Borrego Desert State Park, California








 Dan's Journey through Prostate Cancer
