Month 90 – A Date with the R.O.

The week after my visit with the urologist last month, I had to relocate my office at work temporarily while the facilities team upgrades the HVAC system in our permanent offices. As I was setting up my new desk, I glanced up and saw this pinned to the bulletin board, apparently left by the previous occupant:

IMG_20180501_164755468_HDR (1)

Coincidence? Yep. But the timing couldn’t have been better.

I do believe that a positive outlook is helpful in situations like this, but with a healthy dose of reality thrown in for good measure. We can all “do our worst” in combating this disease, but the reality is that the cancer is in the driver’s seat. Yes, we can be proactive in doing our research and selecting our path, but we’re always reacting to the latest test result or the efficacy of the last treatment option.

Me doing my “worst” in the last three weeks has been slogging my way through the Veterans Affairs (VA) administrative logjams to get my appointment scheduled with the radiation oncologist. I finally got my appointment set up yesterday.

In a nutshell, the urologist forgot to hit the “submit” button for the referral. It took three weeks of emails and phone calls to figure that out, but we made it. The urologist was truly apologetic in his email to me. I get it. We’ve all made similar blunders. No harm, no foul.

My appointment is next Thursday, 17 May 2018, but there was a surprising twist in it.

All of my appointments with the urologists have been at the VA Medical Center in La Jolla (San Diego), and I was fully expecting my appointment with the radiation oncologist to be there as well. After all, it is the preeminent VA medical facility on the West Coast. Silly me.

The appointment is at Naval Medical Center San Diego. The twist? I work at Naval Medical Center San Diego—seventy-five steps (I counted) from the radiation oncology department. I pass the department twice a day on my way to or from my car, and I always thought to myself as I passed, “Someday I may be in a place like this.” Little did I know that I would be in that specific place!

Of course, the first thing we need to do is answer a boatload of questions before making the decision to get zapped. That’s the purpose of this initial consult, so I’ll be working on that list this weekend and next week.

Stay tuned.

Day 2,722 – No Probability for Me

I’m one of those people who always thinks of a snappy comeback—three days after the conversation.

Over the weekend, I reflected on my conversation with the doctor last Thursday, and one of the things that I failed to ask was what probability he would assign to the notion that my increasing PSA is attributable to benign residual prostate tissue instead of returning cancer. I sent an email that asked specifically:

I fully understand that none of us have a crystal ball, but the one thing that I failed to ask Dr. is what he thought the probability of this being benign residual tissue was. Is it 5%? 25%? 50%? His experience gave him the insights to make the comment, so his experience may also be able to measure the likelihood as well.

To which he replied:

I’m afraid I am not able to assign a percentage likelihood to the chance that any residual tissue is benign. I can only really extrapolate from the rate of change in the PSA. The longer it took to be detectable and the slower it rises, the more it seems likely to be a bit of benign tissue. Either way, it is those lab values and their pattern that will help to guide treatment. If it rises quickly then will treat, since a) that pattern is more likely cancer, and b) if it’s not cancer it is acting like cancer and the stakes are too high to disregard even with a high % prediction at this point that the tissue is benign.

Hope that helps!

Dr.

His comment, “…b) if it’s not cancer it is acting like cancer and the stakes are too high to disregard even with a high % prediction at this point that the tissue is benign,” seems to be all over the place and contradicts his opening statement of not being “able to assign a percentage likelihood.” Hmmm…

So that was an interesting little exercise. I really didn’t expect him to come back with a specific number, but I thought I’d ask anyway. I don’t know that his answer convincingly persuades me one way or the other, but it does allow me to throw a tad more weight behind his theory that this is benign. A tad.

Bottom line: The only thing we know with any certainty is that my PSA continues to climb. Beyond that, it’s all a freaking guessing game.

On a related note, I’ve yet to hear from the radiation oncology department with an appointment for me. If I don’t hear from them tomorrow or Thursday (a crazy day at work for me), I’ll try to call on Friday to get on the calendar.


UPDATE:

About an hour after posting this, I came across this little gem of an article from 2005:

The presence of benign prostatic glandular tissue at surgical margins does not predict PSA recurrence

Key points:

We conclude that the presence of benign prostatic tissue at the surgical margins is not associated with adverse prognostic features and does not have prognostic relevance; therefore, we do not advocate reporting the presence of benign prostatic tissue at the inked margins as a standard part of the surgical pathology report on prostatectomy specimens.

Because benign epithelium at surgical margins is not correlated with postoperative PSA rises, postoperative PSA increases should in most cases continue to be considered “biochemical failure”.

Obviously, that’s not good news and certainly warrants more research.

This article from 2013 calls a few things into question:

Benign Prostate Glandular Tissue at Radical Prostatectomy Surgical Margins

Key point:

The most interesting finding of this study is the identification of Benign Glands at the Surgical Margins (BGM) after both Open Radical Prostatectomy (ORP) and Robot Assisted Laproscopic Radical Prostatectomy (RALRP) was not associated with recurrence, either biochemical or clinical, during a median follow-up interval of 49 months after ORP and 28 months after RALRP.

Extending followup further should clarify whether BGM leads to low, detectable levels of PSA that may not meet threshold for defining biochemical failure. This may be particularly relevant with the widespread availability of ultra-sensitive PSA assays. The routine use of ultra-sensitive tests after treatment has not been validated and remains controversial in clinical practice, and may be particularly true in patients at low risk of disease recurrence and potentially in those with BGM.

Within our cohort, longer follow-up may reveal detectable levels of PSA associated with BGM that may not reflect actual prostate cancer recurrence but rather a clinically benign elevation of PSA.

In other words, there’s more research to be done.

Day 2,703 – PSA Results

The bad news: My PSA continued its upward climb to 0.11 ng/ml. The good news: The rate of increase remained constant (and is still quite slow).

The result is exactly where my spiffy spreadsheet said it would be, so I’m not overly surprised. All that’s left to do now is wait for my appointment with the urologist on 19 April. I’ll have to do my best to let him speak a little before I assault him with my already prepared list of questions.

This result reinforces my belief that it’s time to bring a radiation oncologist into the discussion so I can get his or her perspective on salvage radiation therapy, especially regarding the risks of long-term side effects impacting quality of life and the likelihood of success.

More to come…

PSA 20180405

Month 87 – Adapting and Researching

Ever since my December meeting with my doctor to review the latest uptick in my PSA reading to 0.10 ng/ml where he told me I need to begin to think about salvage radiation therapy, it’s as though the clock has been turned back to when I was first diagnosed. That makes this all very real once again. We’re getting closer to having to make a decision to move from monitoring to action.

My emotions have been all over the place—from mad as hell at the world to ready to bawl at the drop of a hat—and I felt compelled to research as much as I could, as fast as I could even though my next PSA and doctor’s appointments aren’t until April. On the good news front, the peaks and valleys on the emotional roller coaster have diminished some over the last two months. They’re still there, but not as bad as they initially were.

IMG_4828
San Diego at Night

I’ve been spending a good amount of time (perhaps too much) researching and hanging out in the advanced prostate cancer section of various online support groups. That’s been both helpful and a tad frightening. It’s been helpful because I’m new(er) to the advanced prostate cancer discussion, and I’ve been learning more about the different treatment options, protocols, and latest research. It’s been frightening because reading the first-hand stories—while valuable and necessary—has stoked my fears of the treatment side effects.

I did come across one thing in my research that I’ll definitely discuss with my doctor in April.

We know biochemical recurrence after prostatectomy has been widely defined at 0.2 ng/ml for quite some time, yet more and more research is indicating that salvage therapy should begin early in order to have the best chance of success. Some suggest starting SRT before hitting the 0.2 ng/ml threshold.

Of course, as we all know in the field of prostate cancer, nothing is clear-cut. You can easily find research that has conflicting recommendations.

I came across Stephen J. Freedland’s 2005 study (co-authored by Alan Partin and Patrick Walsh—heavy hitters in the prostate cancer world from Johns Hopkins) that shows I may not have to do anything other than continue to be monitored given my status (PSA = 7, PSADT > 15 months, time to recurrence > 3 years). In fact, he writes:

“It is amazing to me that for a man who has all the low-risk features – if his PSA doubling time is greater than 15 months, his Gleason score is below 8, his PSA comes back after three years – his odds of being alive 15 years later are 94 percent.” These men do not need treatment, he adds. “If we know that 94 percent of these men are alive and well 15 years after surgery with no further treatment, anything we do to treat them is unlikely to improve on that, and probably would only affect the quality of life.”

That’s quite encouraging for someone fearful of side effects and loss of quality of life. Combine that with the Pound study done in 1999 that said it takes on average eight years to metastasis after BCR and, on average, another five years to death after metastasis without any additional treatment, and you’re building a stronger case for doing nothing other than continued monitoring for those of us who are averse to treatment side effects. At least in my mind at the moment.

You can read an abbreviated summary of the Freedland study in the Johns Hopkins newsletter, Prostate Cancer Discovery, here, and the full study as published in JAMA here.

I’m slowly adapting to this new path that I’m on, and I’ll work to find the right balance to stay away from the online support groups and the Google machine to maintain a sense of sanity. I fear, however, that controlling the emotional roller coaster is going to be far more challenging from this point forward (steer clear or pass the tissues). Just a hunch.


One related footnote. I’ve not yet met with a radiation oncologist since my PSA started going up in September 2015. If it stays the same or goes up again in April, I’ll ask the urologist for the referral just to start the conversation and learn more from his/her perspective.

Month 86 – Struggling

First things, first. I’m struggling to thaw out after spending five days in frigid (-4° F / -20° C) Chicago with my sister and her family this past weekend. You may well be asking, “Who in their right mind flies from San Diego to Chicago in January?!?” Sadly, that would be me.

I contemplated returning for Christmas but had sticker shock on the cost of the airfare, so I opted to return for my birthday last week at a quarter of the cost. This birthday was one of those annoying milestone birthdays—the 30th anniversary of my 30th birthday—and that definitely warranted an appropriate celebration. Of course, anyone in our situation knows that any birthday you’re around to celebrate is a good birthday.

But what I’m really struggling with is this whole notion of recurrence and what to do about it.

I’d like to think that throughout my life I’ve been a generally optimistic, my glass is half full kind of guy, but one with a healthy dose of reality attached to that optimism. Hope for the best, plan for the worst, and recognize the inevitable. I understand the value of a positive attitude, however, I’m increasingly finding that I have a diminishing tolerance of false optimism. “You got this. You’re going to kick cancer’s ass!” Really? Are you sure about that? How do you know? And at what cost? The $109,989.11 invested in my prostatectomy (the real number, mostly paid by the insurance company) doesn’t seem to be paying off.

The costs that I’m talking about aren’t just financial, either. There are emotional and physical costs as well.

With salvage radiation therapy (SRT)—the only option that still has a curative potential—there’s the risk of increased incontinence, loss of sexual function, bowel control issues, and fatigue during the treatments. Chatting with other patients in online forums or through their own blogs, some of these issues don’t manifest themselves until well after the SRT treatments end. And all of this for a 30%-55% chance of having no evidence of disease five or six years after SRT ends.

With androgen deprivation therapy (ADT) (hormone therapy), there’s the loss of libido and sexual function, mood swings impacting relationships, hot flashes, loss of muscle mass, increased risk of osteoporosis, and significant depression. Of course, ADT is not curative, so you get to suffer through those substantial side effects for a longer period because ADT prolongs your life.

It’s easy to get excited when you see your PSA plummet after starting ADT, as it impacts those androgen-dependent cancer cells. But guess what? There are also androgen-independent cells floating around that the ADT won’t impact at all, and it’s those cells that will start driving the PSA back up again and that will ultimately kick your ass.

Being a data-driven numbers guy, I’m also struggling with how to quantify these potential impacts on quality of life.

When you’re in an online or even in-person support group, you have to remember that there’s a self-selection bias taking place that will skew your perspective to the bad. Think about it. Almost everyone who’s in the group is there because they’re at some stage of dealing with this disease and having issues that need answers. Who you don’t see are those patients who are outside of the group who have success stories in dealing with their cancer and have simply stepped away from that chapter of their life.

For me, I want to know the ratio of who’s in the group versus those who are outside the group. Is it like an iceberg with 10% of the patients in the group being the visible ones and 90% of the success stories out of sight? Is it 50-50? 30-70? 60-40? Knowing the answer to that helps me understand the risks better.

I’ve stumbled across a few studies that talk about the likelihood of potential side effects from SRT but I would like to see more. The risks do seem to be relatively low from what I recall and from what my doctor is telling me, but forgive me if I’m skittish about accepting even low risk given where I’m at. (My surgeon forewarned me that there was a 20% chance the cancer would return; I guess I’m just not feeling all that lucky at the moment given my track record.)

Similarly, with ADT, it seems that most everyone suffers some form of side effects, but each person is impacted differently. Again, the numbers guy in me would love to see some sort of study that says, “While on ADT, my quality of life has been reduced by __% in each of the following areas…” I’ve heard patients say that they are “just a shell of the person I was once” or that the ADT has them remaining in bed 20 hours a day. Of course, there are others who seem to have only mild side effects with negligible impact on their daily lives. What’s the distribution like between those two extremes? Knowing the answer to that would be very helpful in decision making.

Given all that, I’m struggling with one more thing, and it may scare or even offend some readers.

“You’ve got plenty to live for. You need to fight. You need to be strong. You need to be a warrior and defeat this disease,”—all things that I’ve heard along the way. There’s this pervasive attitude that other patients, family members, and the healthcare system have that we must do everything we can to go on living for as long as we can at all costs.

Why?

Please don’t panic and think that I’m ready to check out tomorrow. I’m not. There is plenty to live for, and that is precisely why I ask the question.

Is being a shell of yourself and staying in bed 20 hours a day really living, or is it merely existing? Would you rather live a more full, active life for 8-10 years, or merely exist for 20 years?

What about the impact on your significant other and those closest to you? Yes, they’ll be by your side every step of the way. Do you think they would rather remember your last years as being present and engaged for 8-10 years, or withdrawn, moody, depressed, and barely capable of functioning for 20 years?

What about the financial impact on your family? Would you rather take a few bucket list trips with your significant other and family in your remaining 8-10 years, or would you rather take out a second mortgage on your home to pay for the drugs and latest technology tests that will keep you existing for 20 years, placing a financial burden on those who survive you?

Before you send me all sorts of hate mail, I know those are extreme examples and that there are many shades of gray between the extremes, but, in the absence of studies or data that mitigate those examples, that’s what’s rattling around inside my analytical, pragmatic mind at the moment—right or wrong. It’s just the way I’m wired. The good news is that I have time to find those studies and data that hopefully will give me the information I feel I need to make decisions going forward.

It takes strength to go through the radiation, ADT, and chemotherapy if that’s the path that you choose. It also, however, takes strength to say, “No. I’d rather live without those debilitating side effects for as long as I can, even if it means it will be for a shorter period of time.”

Thirteen years ago, my mother was diagnosed with mesothelioma, the incurable cancer associated with asbestos exposure. She was given the option to participate in some clinical trials that may have extended her life three to twelve months, but she refused. “I don’t want to be someone’s pin cushion when the end result will be the same.” She wanted to retain control over her life for as long as she could, and she did so to the best of her ability. Sadly, though, it was only a matter of months before she died, but she went out on her own terms.

That’s how you kick cancer’s ass.

I would like to think that I’ll be able to do the same.


Just a note. Because I knew I would be traveling, I wrote this post over a week ago. While I was in Chicago, a fellow prostate cancer patient, Mark Bradford, replied to a question in an online support group, and it’s complementary to the topic of this post. The question posed was, “At what point do you get tired of fighting?” He replied:

I dislike framing this as a fight. You have a disease, and you seek treatment for [it] till you decide to stop. Being in treatment is not fighting and stopping treatment is not giving up. I was inoperable from the beginning and stage 4 soon after. My outcome was certain, so my priority was quality of life over quantity. I did HT [hormone therapy] until it stopped working, and cannabis oil throughout. I refused chemo as it would not cure me or significantly extend my life. Don’t let anyone say you’re giving up if you decide it’s time to stop treatment. I could not afford alternatives, so my choices were limited. If you have the means, do whatever seems right to you. But accepting reality is not giving up.

I don’t think that I could agree more with Mark’s comment about framing this as a fight and about being in treatment or stopping treatment.

Mark is nearing the end of his life, and you can read his very poignant blog, God’s 2 by 4: Mark Bradford’s Cancer Journal.

Another patient, Dan Cole, answered simply and succinctly: “Live the life you choose to live. That is winning the fight.”

I know I’m getting way ahead of where I should be given my current status but, if nothing else, this disease certainly causes you to prematurely contemplate your own mortality.

Life After Radical Prostatectomy: 84 Months Later

So it’s been 84 months since my radical prostatectomy. How am I doing?

Status

With my PSA increasing steadily over the last two years to the point where it’s now at 0.10 ng/ml, it appears that I’m on the path to recurrence. Needless to say, that’s not the outcome that I had in mind when I started this journey, but my surgeon did warn that approximately 20% of prostatectomy patients have the cancer return.

Emotions

My visit to the doctor in December went just as I expected it would, with one exception. I left the office feeling as though the wind had been knocked out of me. This whole notion of recurrence took on a whole new meaning when the doctor suggested that we’re going to have to start thinking about radiation in the future. It’s becoming real again. Since then, I’ve been doing okay. Not great. Not horrible. Okay.

Incontinence

I remain “dry” 98% of the time. There have been a few very long days at work where my body tired and, combined with the physical exertion at the end of the day, I was a bit more prone to leak. Rarely do I need to get up to go to the bathroom in the middle of the night—I can last 6-7 hours most nights.

Sexual Function

I continue to do so-so in the ED department. Remember, I have only one nerve bundle remaining, but I can get an 80%–90% erection most of the time. Some days are better; others are worse.

I do find that my libido is still there, and there are times through the day where I can feel things stirring down below. Not enough to obtain a natural erection—those days are gone—but enough that with a little stimulation, it would be much easier to achieve an erection.

Summary

Recurrence is the fear of every cancer patient because now your options become more limited and the costs of dealing with it—emotional, physical, and financial—begin to increase significantly. It’s time that I start seriously preparing for the trip down this fork in the road. The good news is that I have time with my PSA doubling time as long as it is.

Day 2,583–PSA Results

PSA 20171204My December PSA results came back just as predicted by my spreadsheet’s silly little trendline: 0.10 ng/ml.

The bad news is that it keeps climbing; the good news is that the doubling rate appears to be about 16 months. My follow-up appointment with my doctor is 19 December 2017 where we’ll probably agree to continue to monitor every 3-4 months for the time being.

Interestingly, from an emotional perspective, this has been pretty much a non-event for me. I’ve resigned myself to the fact that the likely explanation for the increasing PSA is the return of the cancer, so at this point, it’s only confirmation of something that I already suspect/accept/know.

That’s it for now. I’m sure I’ll have more thoughts in this month’s regular post on 11 December.

Month 81 – PSA Threshold for Salvage Therapy Survey Results

In last month’s post, I asked readers to complete a short survey to get a better idea of the PSA threshold that would dictate the beginning of salvage therapy. The survey asked:

  • How their medical teams defined “undetectable” PSA levels.
  • How their medical teams defined biochemical recurrence after a prostatectomy (what PSA level).
  • At what PSA level did they and their medical teams decide to begin salvage therapy.
  • How long after PSA biochemical recurrence was it before salvage therapy began.

Before going into the results, I first want to thank those who took the time to participate. You may view the results using the link below:

Salvage Therapy Treatment Survey Results

I could have designed the survey better. I probably should have asked for post-surgery Gleason score and pathology to see if there was a correlation between a higher Gleason score and acting earlier at a lower PSA level. The sample size is small enough where it’s not statistically significant, but there were some interesting observations:

  • The definition of “undetectable” generally ranged from <0.01 to <0.1 ng/ml. I believe that to be a reflection of whether the traditional PSA test or the ultra-sensitive PSA test is being used.
  • The consensus for the definition of biochemical recurrence seemed to be 0.2 ng/ml.
  • The PSA level at which some sort of salvage therapy began was widely spread between 0.17 ng/ml and 3.5 ng/ml.
  • The time to begin salvage therapy after biochemical recurrence varied from one to 35 months.

[Note: I’ll keep the survey open for a while longer and new responses may skew the summary above.]

For me, there aren’t any real “A-ha!” findings that provide clarity, and I expected that going into this exercise. The only thing that’s clear is that each case is unique—from both the patient’s perspective and the medical team’s perspective—and that means that my numbers will be different from your numbers and those will be different from Sam’s numbers and all of us will act (or not) on those numbers differently.

It is nice to know, however, that my medical team is in alignment with others on some of the measures.

And just to prove that I’m not nuts obsessing over the definition of biochemical recurrence, a somewhat dated research paper (2007) showed “a total of 145 articles contained 53 different definitions of biochemical recurrence for those treated with radical prostatectomy….In addition, a total of 208 articles reported 99 different definitions of biochemical failure among those treated with radiation therapy.” [Emphasis added.]

No wonder there’s confusion among us patients!

For me, the key statement in that paper was, “The Panel acknowledges that the clinical decision to initiate treatment will be dependent on multiple factors including patient and physician interaction rather than a specific prostate specific antigen threshold value.”

It’s up to us.

Day 2,460 – The Day After

It’s Saturday morning, I’m up, and the birds are chirping outside the window. All good things.

The other good thing is that, for now, I’m remarkably at peace with last night’s PSA results. There’s no anger. No sadness. No real fear. That’s a good thing, too. Wasting emotional energy won’t do anything to change the result.

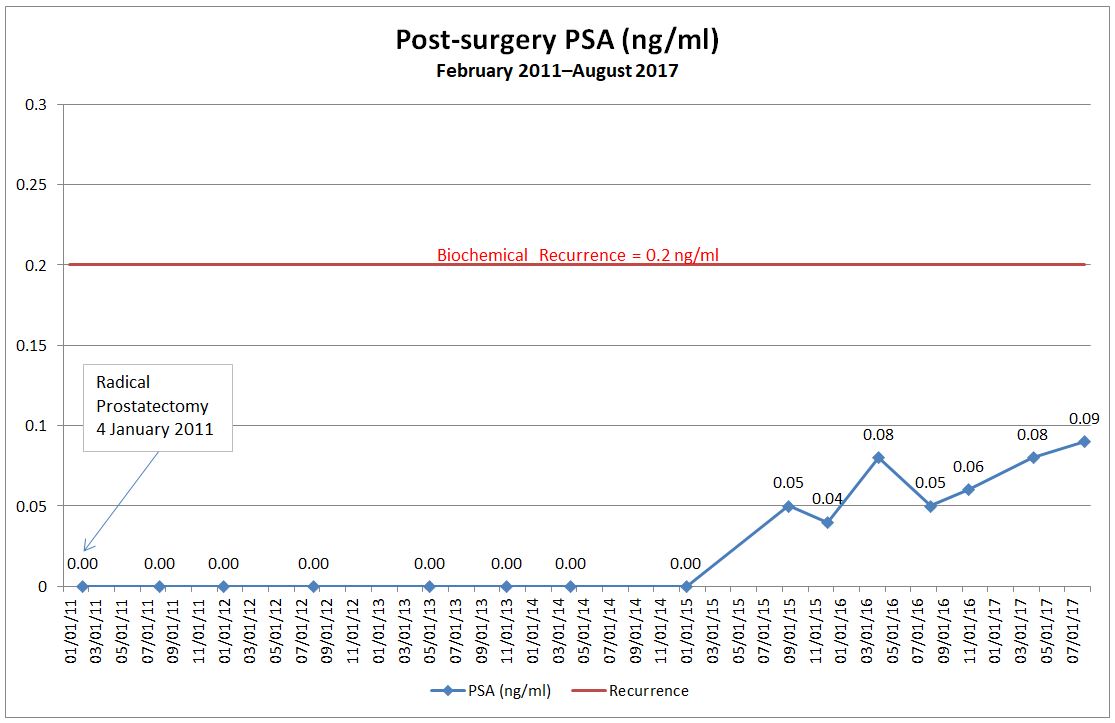
Another good thing is that it’s taken two years for my PSA to get to this point, and it may take another two years before it hits the traditional 0.2 ng/ml recurrence threshold. That’s time, and time is a good thing.

So what’s next?

My appointment with my doctor isn’t until 12 September and we’ll have a lengthy discussion then. I’m okay with the delay; it allows me time to put together my questions and concerns.

One of the concerns that I will raise yet again is the PSA level at which recurrence is defined. For years, the 0.2 ng/ml threshold has been the accepted standard. However, based on more recent studies, it’s becoming increasingly accepted in the prostate cancer world that salvage treatment should start much earlier.

Studies out of UCLA and Johns Hopkins suggested that a PSA of 0.03 ng/ml using the ultrasensitive PSA test can be predictive of recurrence. In that case, I’m about 18-24 months behind the 8-ball. Another study out of Germany released in May 2017 suggested recurrence be defined at 0.1 ng/ml, which I’m just shy of (time for one more Maß of beer at Oktoberfest!). And just to prove that I’m not nuts obsessing over the definition of biochemical recurrence, a somewhat dated research paper (2007) showed “a total of 145 articles contained 53 different definitions of biochemical recurrence for those treated with radical prostatectomy.” [Emphasis added.] No wonder there’s confusion among us patients!

You can see why, then, it’s so confusing and frustrating when recurrence is being defined by different groups as anywhere between 0.03 ng/ml and 0.2 ng/ml and your numbers are smack-dab in the middle of that range. Either my cancer is back or it’s not. It just depends on who you ask.

For my own sanity at this point, it’s just easier for me to accept the idea that the cancer is back, period. I can’t keep going on the emotional roller coaster ride of “Is it or isn’t it?” Given two years’ worth of upward-trending data points when there shouldn’t be any PSA at all, it’s a fairly safe bet that the cancer is back. I genuinely don’t think I’m getting ahead of myself and, if I’m proven wrong at some point in the future, I’ll eat my words and we’ll have one hell of a party. (Oktoberfest, anyone?)

Treatment options for me include salvage radiation therapy (SRT), androgen deprivation therapy (ADT) (hormone therapy), a combination of both and, perhaps chemotherapy. There are also newer options out there that I need to get more familiar with. Of course, there’s always the option to do nothing, too (it’s not as crazy as you think).

Salvage Radiation Therapy

Radiation therapy usually targets the prostatic bed—where the prostate used to be—on the assumption that that’s where the residual cancer cells are hanging out. But the insidious thing about prostate cancer is that microscopic cells could be anywhere in the body and never get picked up by any scans or imaging. You can blast the crap out of your prostatic bed—risking increased incontinence, complete impotence, and bowel control issues—but not get all the cancer. In fact, one study shows that only 38% of SRT patients are disease-free at five years after their radiation therapy. Other studies put the number at around 50%. SRT can be curative, however, in those patients where it worked.

I’ve also seen conflicting guidance about SRT. On the one hand, “men with Gleason scores of 7 or lower, no cancer found in their seminal vesicles and lymph nodes, and increases in PSA several years after surgery were more likely to have a local recurrence of cancer—which means their cancer may still be cured with external-beam radiation to the prostate bed, where some residual cancer cells may be hiding.” (Walsh, 2nd ed. 381) I fit all of those requirements and would be a candidate for SRT.

On the very next page in Walsh, however, it states, “Radiation was also not likely to help men who had negative surgical margins. This is logical…because patients with negative margins whose PSA persists after surgery are more likely to have residual disease outside the prostatic bed, as opposed to those whose margins were positive at surgery, where disease is likely to remain in the area (and thus can be treated with radiation).” I had negative margins. The one thing that troubles me in that passage is the word “persists” because it implies the patients’ PSAs never went to undetectable after the surgery like mine did. That may make a difference in applicability.

Then there’s this little tidbit of information from the New Prostate Cancer Infolink: “There is an open controversy as to whether salvage radiation therapy, even if given after biochemical recurrence (a confirmed PSA ≥ 0.2 ng/ml), translates to a survival benefit. Fewer than a third of patients with a post-prostatectomy biochemical recurrence experienced systemic progression, and it takes a median of 8 years for distant metastatic progression, and 13 years for mortality to occur, according to a Johns Hopkins study (by Pound et al.).”

Androgen Deprivation (Hormone) Therapy

Prostate cancer feeds off of testosterone, and androgen deprivation therapy is a means of starving the cancer cells of testosterone. It’s the equivalent of chemical castration. There are two types of ADT: one stops the production of testosterone and the other stops the cancer cells from absorbing the testosterone. But here’s the kicker: there are androgen-independent cancer cells out there that will not be affected at all by either therapy, and they’ll just keep growing. ADT is not a cure; it only prolongs life.

ADT has some nasty side effects: depression, fatigue, hot flashes, anxiety, increased risk for other diseases (diabetes, cardiac issues), weight gain, osteoporosis, loss of libido, irritability, and others. Some of these side effects are so debilitating in some patients that they can no longer work and have difficulty functioning in their daily lives. (Yes, that’s a worse case scenario, but from my anecdotal observations of ADT patients online, side effects do have a significant impact on many of them.)

Another option to eliminate the majority of testosterone production is through surgical castration (gulp!). That may reduce some of the side effects, but not all.

Lastly, there’s debate as to when to start ADT and how to administer it. Some argue that you should start early to slow the growth; others argue that you wait until the end so that it can be helpful in tumor and pain management; yet others argue between whether it should be administered continuously or intermittently. Interestingly, studies have shown there is no statistical difference in outcome whether you start ADT early or late—the result is the same. (Walsh, 2nd ed. 473, 476-477) The only difference is that, if you start early, you suffer from the side effects for a much longer period.

Doing Nothing

Of course, the last option of doing nothing has some merit, too.

I’m not keen on being radiated, especially if we don’t know without a high degree of certainty that the cancer is still in the prostatic bed. I mean, really, if I’m going to risk peeing and pooping in my pants and never having an erection again for the rest of my life (perhaps slightly exaggerated) for just a 38% chance that I’ll be cured… That requires some thought.

The same thing with starting ADT early. If you’re going to be depressed, curled up in a bed 20 hours a day, unable to work or function just so you can extend your life for a few months or years, and the outcome is going to be the same as if you started ADT late, is that really worth it? Is that living?

None of us are getting out of here alive, and doing nothing isn’t “giving up.” In fact, when the side effects of the treatment may be worse than the disease itself, I view doing nothing as a way to say, “F–k cancer!” If I can squeeze a whole lot of living into the next 10-15 years without side effects of treatment impacting my quality of life and preventing me from truly living, why wouldn’t I do that? Sure, it’s a crappy hand that I’ve been dealt, but I’ll just come to terms with it and play it out. Again, none of us are getting out of here alive, and the notion of extending life at all costs just for the sake of extending life doesn’t sit well with me. Quality over quantity is important to me, and I’m sure there’s a balance in there somewhere.

A study done in 2005 at Johns Hopkins looked at various factors—Gleason score, PSA doubling time, and time from surgery to the return of PSA—and determined the likelihood that you will not die from prostate cancer based on those measures. Based on my numbers (Gleason 7, PSA DT more than 10 months, and return of PSA more than 3 years after surgery), I have a 99% chance of being around in 5 years; a 95% chance of being around in 10 years; and an 86% of being around in 15 years. (Walsh, 2nd ed., 386-390) Again, what’s not clear from that summary is what, if any, treatments patients had during that time. Bottom line: I’m not going anywhere anytime soon.

Have I come to a decision? Of course not. It’s far too early and there are far too many conversations that need to be had with medical teams, and much more research to do. It will also be interesting to see if we stick to the four-month PSA test cycle or increase the frequency now. Based on my last conversations with the VA doctor, I suspect that we’ll keep to the four month cycle and consider acting once the PSA hits the 0.15 mark or so. (They’re pretty tied to the 0.2 ng/ml number.)

The one thing I want to understand much better is what percent of patients are impacted by the treatment side effects and to what degree. I’ve already got a decent idea—the numbers are relatively small—but I need to zero in on that in my research.

One last bit of good news. Advances are being made in prostate cancer research every day, and perhaps there’s something in the pipeline that will be of use in the near future.

At least now you have a better idea of what’s ahead and how my pea-sized brain is processing all of this at the moment.

It’s now well into the evening here in San Diego (took a break in the middle of the day) and time to figure out where those chirping birds went to escape the heat. That, or plan a trip to Oktoberfest.

[I hope I didn’t offend or scare anyone.  I also respect each and every person’s decision for their own treatment options because what they chose is right for them and their personal circumstances.]

Day 2,459 – PSA Results

My silly little trend line that I slapped on my PSA tracking chart wasn’t so silly after all. It was dead on target. My latest PSA: 0.09 ng/ml.

Crap. (Or some other four-letter expletive.)

Even though I expected this (thanks, trend line), I’m still absorbing the significance of yet another increase in my PSA.

In a way, I’m glad to see the results that I have. Certainly not because I want the cancer to come back, but because it removes some of the doubt caused by the yo-yo readings last year. Now I can come to terms with the likelihood that I really am headed down the recurrence path, and I can focus on what’s ahead.

So those are my thoughts in the first 30 minutes since seeing the results online. I’m sure there will be more thoughts to follow. I have to admit that I’m unusually unemotional about this at the moment. That’s good.

I’m sure I’ll have more thoughts to share once this sinks in.